The fact that we have three highly effective vaccines in such a short period is amazing and between them we might stand a chance of making and distributing them at the scale necessary to get things under some kind of control by August.
Pandemrix, a flu vaccine, caused a notable uptick in narcolepsy in Sweden, Finland and likely the UK. This was not (and could not) be seen in smaller trial populations.
It is not a given that any of the covid vaccines is safe enough. Historically, two cases of rushed vaccines (cutter polio and Gullah barre) were worse than the disease - and these were for diseases worse than covid. Those were 50-60 years ago. Pandemrix was 10-20. I’m not sure we’re that much better on safety now to rush vaccines.
So if you give the entire US population a vaccine like that, less than twenty thousand of them develop narcolepsy. As a reminder a quarter million of them already died from COVID-19 and more are dying every day - not to mention the tens of thousands whose cause of death isn't listed as COVID-19 but would not be dead if not for an ongoing pandemic.
Cutter screwed up. No amount of prior safety testing can fix that. Their Polio vaccine had Polio virus in it (to be clear: The traditional Oral Polio Vaccine is supposed to have a "live" virus in it, but the injected vaccine Cutter were selling is not). Obviously nobody is going to test "What happens if we inject children with the Polio virus" because the answer is "Some of them get Polio. Duh" and so no test could have prevented Cutter from screwing up.
I have no idea what you meant by "Gullah barre" the Google results I get are all about Guillain-Barré syndrome, which I mentioned above. Guillain-Barré is not a vaccine, it's a weird auto-immune disorder, and arguably even where it's listed as very rare side effect of a vaccine, that's misleading because it's also a side effect from getting viral infection, so if you avoid vaccination but do get the virus you may get GBS as a result anyway. The human immune system is pretty inscrutable.
I assume the concern is that an unknown unknown means it could cause/trigger/amplify some other disease/condition that may be comparable/worse than the problem it solves.
Cause/effect and morals are hard. Add to the mix a general statistical innumeracy, and some general suspicion about authorities, and it makes it really hard for the general populace to actually weigh the two different options.
I don't think we should dismiss these concerns as just stuff for nutjobs. I've seen otherwise reasonable people having trouble making up their minds about that.
And yes, the mechanism is likely that Pandemrix activated a predisposition. But it was not activated in statistically equivalent kids who did not get Pandemrix.
Why is it so hard to acknowledge that not all vaccines are perfect, and that there’s a risk involved? I am not avtivax. I am pro vaccination. I am anti religious “a vaccine can never be bad” thinking which seem to be prevalent among otherwise rational scientific people.
This is just patently untrue.
The Cutter Incidence gave patients Polio due to an improperly activated virus. While this is bad, it could not be worse than the disease itself - since it is the disease itself, no worse, no less.
Regarding risk of Gullain-Barre syndrome due to vaccination, Wikipedia has this to say: "In fact, natural influenza infection is a stronger risk factor for the development of GBS than is influenza vaccination and getting the vaccination does reduce the risk of GBS overall by lowering the risk of catching influenza." So here I also find it hard to believe the vaccine would be worse than the disease,
I'm also sceptical of the claim that Polio or the 1976 Swine Flu would unambiguously be worse than Covid19. 70% of Polio case have no symptoms, and less than 0.5% cause permanent injury, according to Wikipedia. The 1976 Swine Flu outbreak seems to have caused a few hundred cases and only one death.
Cutter was, most definitely, much worse than the disease if you look at it from a population perspective.
The 1976 Guilian barre was at least comparable to the flu it was supposed to stop, if not worse. According to https://en.m.wikipedia.org/wiki/1976_swine_flu_outbreak, the disease caused one death and 13 hospitalizations, and an uptick of Giullan barre reports - a disease that more often than not requires hospitalization and sometimes death. I can assure you it caused more than 13 hospitalizations, and - having known two GBS people who made a full recovery - a very long and painful months long process. So, at 50,000,000 immunized - a 1 in 1,000,000 would still be worse than the flu.
I am not anti vax even if HN constantly seems to interpret my comments as such.
I am vaccinated, so are my kids. But whenever I mention that immunizations have risks, I’m treated like a heretic.
Everyone is assuming something like cutter cannot happen again. This is a religious assumption, not a scientific one.
This is a more reasonable assessment, but it is still patently false. According to Wikipedia, 0.04% vaccinations resulted in paralysis in the Cutter Incident, compared to 0.1-0.5% of wild type polio. So the vaccine was 2-10x safer than wild polio. Without vaccinations, virtually all children were infected with polio virus early in life [1], so being administered the defective vaccine was still a lot better than taking a chance with the real disease.
Of course, you are correct regarding the 1976 flu outbreak. If you administer something to a large segment of the healthy population, even a small risk of side-effects will add upp to a large number of cases. If the disease itself turns out to be very rare, as was the case with the flu outbreak, the vaccine itself could cause more damage than the disease even if the disease is much worse.
However, this is clearly not applicable Covid-19, which we already know is spreading very fast and will need to infect a large number of the population before herd immunity is achieved. The situations are simply not comparable at all – even the vaccine from the 1976 flu outbreak would be less risky than the odds of being infected with a serious case of Covid 19 (of which the long term effects are also unknown, to be clear).
> But whenever I mention that immunizations have risks, I’m treated like a heretic.
Mainstream media, healthcare professionals and social media are all worried about the risks of a rushed vaccine. I literally see articles and hear conversations about this several times a month. Nobody is denying that large scale vaccinations have risks.
I'm not criticizing you because I'm against being cautious of vaccination risks. The criticism is that you are spreading false facts and misleading analysis that grossly mischaracterise what the risks of vaccinations really are, both presently and historically.
"Some vaccines can have rare but serious side effects" is a perfectly alright statement. But "Historically, two cases of rushed vaccines (cutter polio and Gullah barre) were worse than the disease - and these were for diseases worse than covid" is just not. Some of it is false and the comparison to Covid19 is misleading.
From https://en.wikipedia.org/wiki/Polio_vaccine#1950%E2%80%93195... : "The Cutter vaccine had been used in vaccinating 200,000 children in the western and midwestern United States.[76] Later investigations showed that the Cutter vaccine had caused 40,000 cases of polio, killing 10.[76]". So, 20% incidence; mentions 250 "paralytic illness", so 0.125% paralysis (no idea where you took the 0.04% - it does not appear in the Wikipedia text).
From https://en.wikipedia.org/wiki/Polio#Paralytic_polio : "In children, nonparalytic meningitis is the most likely consequence of CNS involvement, and paralysis occurs in only one in 1000 cases." ; So, for children, the incidence of paralysis is 0.1%
Who got the cutter vaccine? Mostly children. See e.g. from https://www.washingtonpost.com/history/2020/04/14/cutter-pol... "By April 30, within forty-eight hours of the recall,” Offit wrote. “Cutter’s vaccine had paralyzed or killed twenty-five children: fourteen in California, seven in Idaho, two in Washington, one in Illinois, and one in Colorado."
So, I just tried to check your numbers, and I couldn't; Could you post references?
But I also wanted to check my memory, and Wikpedia seems to agree with me, Go on, please do check my quotes.
still patently false. pfft. Perhaps false under some assumptions, definitely not "patently false".
You would also have to include further transmissions caused by wild polio if you would like to make such a comparison.
> still patently false. pfft. Perhaps false under some assumptions, definitely not "patently false".
Even with your own calculation, which is inflated by also including transmission within the community for the vaccine but not for wild polio, the vaccine was very much comparable to wild polio (0.125% versus approx. 0.1%). Without vaccination, polio would usually infect virtually all children. So even with your own inflated assumptions it's false that the vaccine was worse than polio.
So under which assumptions would it not be false?
Take them with wikipedia, not me. I will note, that Wikipedia talks about both Cutter and Wyeth having problems, so it is possible the numbers are a sum of wyeth+cutter which would be compatible with your numbers being cutter only, but in the context of safety vs. polio wouldn't matter.
> You would also have to include further transmissions caused by wild polio if you would like to make such a comparison.
All wild polio numbers include those numbers by default - there actually is no way to get them otherwise, I guess you are saying "you should probably debase by more than 200,000 because of secondary infections". I don't know how to do that, exactly, but it will likely still be similar.
> Even with your own calculation, which is inflated by also including transmission within the community for the vaccine but not for wild polio, the vaccine was very much comparable to wild polio (0.125% versus approx. 0.1%).
With this calculation, the vaccine was 25% worse than the wild type. No error bars, but, that's easily worse, even much worse.
> So under which assumptions would it not be false?
How kind of you to drop "patently". If you didn't mean "patently" false earlier, why did you use that word? twice?
From[0]: "Patently: in a way that is so obvious that no one could disagree.". It's nice of you to finally bring sources, but even these sources don't make it "patently" false, given that they disagree with the sources I gave (which, I concede, reference more than just the safety of the Cutter incident which I originally mentioned, but which are definitely the subject matter under discussion)
[0] https://www.macmillandictionary.com/dictionary/british/paten...
Wikipedia is not wrong, but you are using their numbers wrong. Your source is talking about the total number paralysis cases that occurred as a result of the vaccine ("250 cases of paralytic illness had occurred"). This includes secondary infections. If you follow the sources listed on Wikipedia page you reference, you will find two sources: my source [1], and [2] (via [3]), both which declare around 60 cases of paralysis in vaccinated persons, and then a larger number (in the order of 200) of total cases. The numbers you reference are referring to only the Cutter polio vaccine, by the way.
And you cannot use the total number of cases in the comparison that you did.
> All wild polio numbers include those numbers by default - there actually is no way to get them otherwise, I guess you are saying "you should probably debase by more than 200,000 because of secondary infections". I don't know how to do that, exactly, but it will likely still be similar.
If by debase you mean divide, then yes: you would need to divide by more than 200,000.
Your number is {how likely am I to get paralysed by the vaccine polio + how likely am I to cause further paralysis via secondary infection chain}, and you are comparing it to simply {how likely am I to get paralysed by the wild polio}. The first number is inflated a lot by the addition of secondary infections.
The numbers are not at all likely to be similar. As you can see in my (and your) sources, secondary infections accounted for more than double the number of paralysis cases, and therefore there it is likely a lot more people got sick via the secondary infections than the number people who was vaccinated. This causes the big discrepancy between our numbers.
Wild polio causes secondary infections as well, but this is not included in the number you are using for comparison, since it only includes the individual risk.
> With this calculation, the vaccine was 25% worse than the wild type. No error bars, but, that's easily worse, even much worse.
But the lack of error bars means that the calculation is meaningless.
You are assuming that "one in 1000 cases" means exactly one case per 1000 cases, and translate this to 0.100% with three decimals of accuracy.
It is clear from context that "one in 1000" is a rounded number for convenience, and they could very well have runded up from 0.8 or down from 1.4. You simply cannot conclude that the vaccine was 25% worse from your data. But we can conclude that they were in some way similar under your false assumptions, as they both would round to 1.
If you want to conclude anything else except "they are both around 0.1%", you would have to find a source that specifies at least 1 decimal of accuracy in the number incidents per 1000 cases.
Of course, this does not really matter, since you would still be comparing the wrong numbers.
Your argument here is "It's ambiguous and inconclusive when using clearly wrong assumptions that inflate the difference". Taking that argument into consideration, I'm still willing to confidently call it patently false.
Although I agree that I should not have said "Even with your own inflated assumptions it's false that the vaccine was worse than polio." What I meant was "Even your own inflated assumptions does not support that the vaccine was worse than polio", but I clearly worded it badly.
> How kind of you to drop "patently". If you didn't mean "patently" false earlier, why did you use that word? twice?
I meant it when I used it, and my question had a purpose. If you cannot give any reasonable assumptions where it wouldn't be false (which you haven't been able to do), then it would be patently false to me. The reason it does not seem patently false to you is because you have several misunderstandings in your reasoning and your reading of the sources. But I'm not really interested in discussing this terminology further.
> given that they disagree with the sources I gave
They don't. As I said, you are simply misreading your sources.
But seriously, even if you would manage to find some source which would refute my sources and back up your original claims, I have a bigger point to make now:
During this discussion, you have made numerous mistakes in many posts, beyond my criticism of your faulty reasoning:
(1) Mathematical mistakes
(2) Misreadings of the sources
(3) Inability to clear up ambiguities by looking at the referenced source or secondary sources
Even if by some happenstance you would happen to be right (even a broken clock, etc), you clearly are not confident enough doing this kind of analysis to be lecturing people about the specifics of vaccination risks. You are just as likely to mislead yourself and others as you are to educate.
Of course, this probably won't stop you, since you are not likely to respect my opinion. But hopefully it will still be in the back of your mind next time you approach this topic.
[1] https://www.nejm.org/doi/full/10.1056/NEJMp048180 [2] https://www.cabdirect.org/cabdirect/abstract/19642705083 [3] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2928990
And I may agree with your analysis - on phone now, can’t really do the reading.
However, we have two sources you claim are only for the cutter incident, whee one quotes 200,000 doses and another 120,000; as you note, the 1/1000 might well be 0.8 or 1.3 in 1000; it may be false but it is definitely bot “patently false”.
On the same note, it’s the internet, and for all you know I am a dog, but I have saved a family members from years of agony and wrong treatments due to wrong diagnosis after being told “it is patently obvious” that my analysis was wrong. And I have apology letters from department heads at two of the world’s highest ranked hospitals after it turned out I was right and they were wrong.
And you know what? I’m quite sure I probably had a few mathematical errors along the way back then as well. But what they thought was two orders of magnitude more probable evidence towards one direction, turned out to be higher probability in the other (by less than an order of magnitude) and turned out to be what the thought was improbable beyond consideration. (And, I found a few mathematical errors in a three peer reviewed papers they were relying on)
I take issue with people who claim “patently obvious” about things which have about factor of 2 or so (if I take your numbers) without error bars (120000-200000 is a large difference) and without supplying sources, which you didn’t bother until I did.
(And I may not have time to delve into this further - this is merely of historical interest to me, not life and death like that other event).
Also, you may notice this sub thread is basically the only one that actually discusses numbers, others use arbitrary determinations like “most people’s living memory” to discard concerns. Despite advocating vaccines myself, I have a problem with religious zealotry around vaccines, which is what most pro-vaccine people practice - I have a child who could not get vaccines for medical reasons for many years, and I have to explain that, no, vaccines are not perfectly safe on an individual basis, and have not historically been perfectly safe on a population basis (Swedish Pandemrix), even though on a net population basis they are a net positive.
I thank you again for your thoughtful discussion.
On the other, a cursory search says the current record for fastest developed vaccine was mumps at 4 years. So this is a vaccine setting new milestones, and there is a risk that not all of them will be positive. I'd rather be a little late to be vaccinated than a little early, especially being in a lower risk demographic.
At the 1-year mark, everything looked perfect. At the towo years mark (original endpoint) the conclusion was that while it was safe, it offered statistically insignificant protection.
Properly designed tests need those 2 years, at the very least. The “SAFE” confidence axis was compromised. Whether or nit it is justified is what we’re discussing here.
Sure, having Guillain-Barre is scary, but it is something that you can make a full recovery from.
It is never an excuse NOT to get a vaccine, unless you actually know that you got Guillain-Barre Syndrome from a vaccine. That is a discussion between that particular patient and their neuromuscular neurologist. In that case, you do not get the flu vaccine any longer because it can cause you to experience Guillain-Barre Syndrome again.
But, this really is an isolated situation that can be categorized as very rare and the general public should always get their vaccines.
If you catch the flu, it can absolutely trigger Guillain-Barre Syndrome, and would be far more likely to trigger Guillain-Barre Syndrome than the flu vaccine itself. If you get the flu and had the flu vaccination, it typically makes the flu illness less worse, making you less likely to get something like Guillain-Barre Syndrome.
There are lots of infectious agents that can trigger Guillain-Barre Syndrome, so it is wise to get your vaccines to prevent them as much as possible. They prevent serious infections, at minimum, which would help prevent Guillain-Barre Syndrome.
I also have the long term variant of Guillain-Barre Syndrome, known as Chronic Inflammatory Demyelinating Polyneuropathy, which is in pharmaceutical remission due to me taking subcutaneous immunoglobulin twice a week for 3 hours each time.
What I am saying is that while all of this sounds rare and devastating, it’s treatable. Not only that, you’re more likely to get Guillain-Barre Syndrome from a bad case of the flu than from a flu shot.
https://www.who.int/vaccine_safety/committee/topics/influenz...
“Even at this stage, it does not appear that narcolepsy following vaccination against pandemic influenza is a general worldwide phenomenon, as no excess of narcolepsy has been reported from several other European states where Pandemrix was used, or from Canada where a pandemic vaccine similar to pandemrix was used. This complicates interpretation of the findings in Finland and Sweden. It seems likely that some as yet unidentified additional factor was operating in Sweden and Finland. The findings from the VAESCO project and further investigations in Finland and Sweden, may help clarify the determinants of any increased risk of narcolepsy, which currently appears to be restricted to the months following vaccination and by age group and country.”
What’s certainly true that for some effects to be observable, millions have to be vaccinated first.
2013:
https://www.reuters.com/article/us-narcolepsy-vaccine-pandem...
“In total, the GSK shot was given to more than 30 million people in 47 countries during the 2009-2010 H1N1 swine flu pandemic.”
“Independent teams of scientists have published peer-reviewed studies from Sweden, Finland and Ireland showing the risk of developing narcolepsy after the 2009-2010 immunization campaign was between seven and 13 times higher for children who had Pandemrix than for their unvaccinated peers.”
“Europe’s drugs regulator has ruled Pandemrix should no longer be used in people aged under 20.”
"The increased risk of narcolepsy due to vaccination was 1 in 18400 or 0.005%."[1] Considering the fatality and long term disability rate of Covid, and the way testing and safety protocols are done for vaccines, I don't really see how there could be an unknown and unseen risk that would outweigh the risk of contracting Covid.
It might be, but it’s not open and shut.
Additionally, it's not as if the average vaccine has a 0.005% chance of giving you narcolepsy. That figure was for the one vaccine in one country which appears to be the only example in most people's living memory of a vaccine possibly causing long-term side effects (it's not even proven the vaccine was the cause). There have been tens of billions of vaccines given during this time period and this is the only example where there may have been long term side effects.
> There have been tens of billions of vaccines given during this time period and this is the only example where there may have been long term side effects.
No, there are other examples, the other two I just mentioned are from memory, I suspect if I go research I will find more (I don't have the time). You know what else is common to those other two cases? They were rushed (pandemrix wasn't AFAIK).
SARS-Cov-2 vaccines were all rushed, and the safety protocols used to confidently ascertain those billions of vaccines were NOT followed - The standard is to wait 2-4 years to see that there's no ADE or other issues.
I am pro-vaccination. I don't understand why it is hard to acknowledge and discuss the risk profile of vaccines - they re not risk free. Excuse me if I don't automatically think a rushed vaccine is perfectly safe.
That Polio vaccine wasn't a side effect of the vaccine though, it was an issue with people accidently getting injected with a live virus. Since no live virus is even remotely involved in any COVID19 vaccines it has zero relevance here. Even if they were, we have 60+ years of history with no similar incidents since then.
> I suspect if I go research I will find more
You really won't. I've been reading about this extensively during this period and those are the only examples where there may have been long term effects that anyone can point to.
I qualified my original comment with "in most people's living memory" and didn't include the '76 swine flu vaccine because, frankly, I don't think pointing to an issue that happened 44 years ago in a field that has seen pretty significant technological advancement in knowledge, methods, and manufacturing processes really makes sense.
> why it is hard to acknowledge and discuss the risk profile of vaccines
My issue is not that there's isn't some theoretical risk, it's that it just isn't put in context of how minute it is. In all likelihood your risk of facing long term effects from a car accident happening on your way to get vaccinated are higher than anything that could happen from the vaccine. And both those risks are, of course, many orders of magnitude less than your chance of suffering long-term effects from catching COVID19.
Your omnipotent knowledge is inspiring. We have absolutely zero years of experience with RNA based vaccines. We had incidents with vaccines, not of the same kind. Ergo, there's a non zero probability we will have incidents in the future, by any reasonable inference.
> I qualified my original comment with "in most people's living memory" and didn't include the '76 swine flu vaccine because, frankly, I don't think pointing to an issue that happened 44 years ago in a field that has seen pretty significant technological advancement in knowledge, methods, and manufacturing processes really makes sense.
That's really painting a target where your arrow landed. Most people's living memory does not include e.g. the 1918 pandemic or the bubonic plague, or atomic bombs, or thousands of other things we're proactively defending against and of which we have better understanding but are still an issue. If "living memory" is your criterion ... well, I wouldn't describe it as anything but completely arbitrary.
Within living memory you have totally understandable and preventable things like Fukushima, the nestle mother milk fiasco in Africa, and others. We had enough understanding to stop all of them, and yet they happened. Every single SARS-COV-2 vaccine manufacturer has gotten government immunity from future claims, which aligns their incentive differently compared to vaccines they have produced in the past. They have become too big/important to sue - much like e.g. the fukushima reactor operator. Given this distinctly different incentive structure, rushed schedule, novel RNA delivery system - your belief that the past is a good predictor of the future is unscientific (at the very least, unbayesian without a ton of nontrivial priors you don't bother stating).
> And both those risks are, of course, many orders of magnitude less than your chance of suffering long-term effects from catching COVID19.
Ah, about that. Do you have any actual data about that? Because the best summary of "long covid" evidence I found was written by an MD, is summarized here[0], and can further be summarized by the word "lacking". I spent a lot of time looking for actual data about long covid (not anecdotes), and this summary is better than what I was able to find myself (but I do urge you to read it - do introduce it to your "living memory").
[0] https://sebastianrushworth.com/2020/11/17/what-is-long-covid...
Apparently the pfizer and Moderna vaccines will keep for 30 days at refrigerator temps after thawing out. You can ship in dry ice and then I can't imagine the vaccine sitting around in any doctors office or pharmacy for longer than 30 days.
Edit: just found a source here confirming what you said: https://www.bbc.com/news/health-55040635
The price difference will likely remain substantial, but in case anyone is unaware, the difference is currently greater due to AstraZeneca pledging to the sell the vaccine at cost "during the pandemic", while Pfizer and Moderna have indicated that they fully intend to profit. [1]
Once AstraZeneca deem the pandemic to be over, the price will likely rise.
It was reported a few months ago that internal AstraZeneca documents showed them projecting the "Pandemic Period" to end on 1 July 2021. [2]
[1] https://www.nytimes.com/2020/07/21/health/covid-19-vaccine-c...
[2] https://thehill.com/policy/healthcare/520202-astrazenecas-no...
These two companies have collectively received more than $1.5 billion from the US government [1]. As I understand it, Pfizer have not taken any federal funding. They do have government purchase agreements, but they are dependent on Pfizer delivering a viable vaccine. Their partner BioNTech received German government funding:
Berlin gave the German company $445 million in an agreement in September to help accelerate the vaccine by building out manufacturing and development capacity in its home market. [2]
[1] https://www.nytimes.com/2020/05/21/health/coronavirus-vaccin...
[2] https://www.bloomberg.com/news/articles/2020-11-09/pfizer-va...
I don’t think the data bears this out exactly. US healthcare tends to optimize for access and quality to the detriment to cost. As the saying goes: access, quality, or cost... you only get to choose two.
The US tends to measure better than any comparable country of its size on those two metrics (and quite poorly on cost...but some of that is because the US funds about 50% of worldwide medical R&D)
https://www.sciencedirect.com/science/article/pii/S014067361...
Edit: U.S. percentage of worldwide R&D has been waning and, while still the largest contributor, is now a little over 40%
And in fact this is one of the big differentiators between 1st world and 3rd world countries: if the population has access to quality services, in health care or other important areas like education and sanitation. The US seems to be designing its systems to become a big 3rd world country.
False: The third leading cause of death in the US is believed to be preventable medical errors. You can go to the best institutions in the US to get care, along with seeing the very best doctors, but you cannot evade a statistic like that, even if you are in the 1%. See: https://www.npr.org/sections/health-shots/2016/05/03/4766361...
Also, this article: U.S. life expectancy will soon be on par with Mexico’s and the Czech Republic’s: https://www.washingtonpost.com/news/to-your-health/wp/2017/0...
Also this: 42% of new cancer patients lose all of their life savings in two years because of treatment. The average amount a cancer patient lost was $92,098.: https://www.insider.com/half-cancer-patients-lose-their-enti...
The truth is that you can be in the top 1%, sitting on a mountain of cash, and still lose an unfathomable amount of money, even while insured, if you have cancer or a rare disease. Both of which are actually common.
It is not the doctors who are the problem here with respect to the medical errors: it’s the healthcare system. A good read on what’s wrong with the system is the short book Our Malady by Timothy Snyder.
If you want to stay alive long term, you may want to consult HealthData.org which analyzes each country’s healthcare systems in depth along with outcomes. The group is world renowned. Ironically, it is also the IMHE group that does the coronavirus statistics that everyone consults.
Personally, I am an American culturally, but I became an EU citizen (Croatia) over the US healthcare system. I never plan on working in the US. I do select the country I am working in now due to healthcare.
E.g., if you don't have insurance you can walk into an emergency room and get treated even if it's not an emergent situation. If you don't have insurance, there is a higher risk you won't pay. That cost then gets spread to others who do.
For example, if someone needs to treat cancer, it doesn't make any good to go to an emergency unit: they will discharge the patient as it is not an emergency situation.
That's because the ER is meant to stabilize a patient, not cure chronic disease. Which is to my point: people will forgo preventative medicine until their condition deteriorates and they need to be stabilized in an ER. People get their non-emergent conditions treated all the time in American emergency rooms.
E.g., if I have diabetes, an ER will not put me on a long-term treatment plan. But if I ignore my disease until I start having hypoglycemic symptoms an ER will treat me until I am stabilized enough to be released. Is this the best system? Absolutely not, but it's much different than saying "only the rich have access to healthcare".
FWIW, I used to work in healthcare, including redesigning ER processes
If this was not enough, hospitals are catching up to the "loopholes" in the law and abandoning poor neighborhoods, to make it even harder for people to use emergency rooms.
https://www.governing.com/news/headlines/health-care-facilit...
You may not understand the nuances of the article you referenced. Take Detroit, one of the cities used to support the claim in the article. The baseline decade used is the 1960s. Detroit has only about a third of the population it had in the 1960s so it's not rational to think they would maintain their previous healthcare infrastructure. Further, much of that population left for the suburbs of metro Detroit, meaning the healthcare facilities being built are just following the population demographics. Add onto that the point that healthcare has changed dramatically over the last 60 years with much more emphasis on outpatient care, and there are rational, non malevolent reasons to decrease the number of urban hospitals
E.g. for myself, I have good insurance, but I don't have a "primary care doctor." I don't go to the doctor unless I'm injured or sick. And I don't mean a sniffle or cough, I mean sick as in I have felt awful for several days.
With that said, it seems to be quite a bit and skewing higher for males than females.
The average American sees a doctor 3 times per year. In France it is 6-7 times per year. In Japan, it’s 13 times per year. This statistic is directly linked to the cost of care.
Canada's HAQ index in 2015 was 87.6 vs. 81.3 for the US. However, Canada spent about $27B US on R&D vs. $495B for the US. On a per capita basis, the US outspends most the world on medical R&D. That drives the US total healthcare costs up while helping to drive down the healthcare quality costs elsewhere. To a certain extent, the US subsidizes the healthcare costs through much of the world, effectively allowing them to optimize for a 2 parameter model while the U.S. must still deal with a 3 parameter model.
I'm not trying to be dismissive, I just don't know how it's germane to the discussion unless we view all the other data through the same lens. The data I linked is per country in absolute and per capita basis that tries to put it in unbiased terms.
Are you claiming the US is disproportionately funding non-useful research? If so, how do we measure "useful" research funding?
[1] https://wtfhappenedin1971home.files.wordpress.com/2020/05/ey...
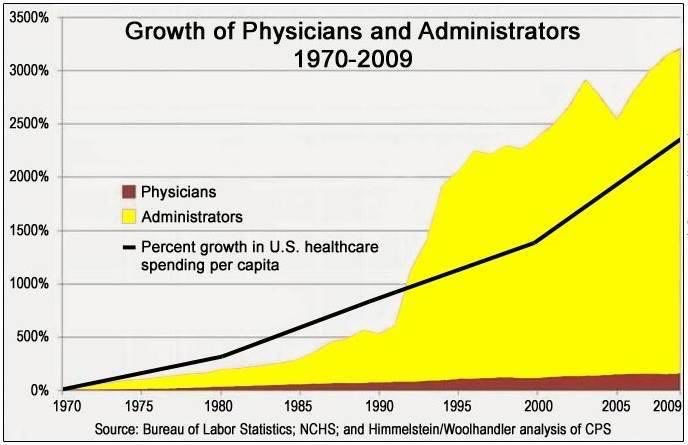
However, the point between comparing countries still holds. If you use older data, you'll see that the U.S. had even more disproportionate R&D funding
I don't think there's a single perfect measure but if you put it in broader context of measures like Nobel prizes R&D spending, patents, etc. it does seem to paint the picture that the US disproportionately contributes to medical innovation.
It's very similar to the measure of health. There is no single great metric. Using a single metric like BMI or blood pressure is flawed. However, you can get a clearer picture if you bring together multiple metrics.
I completely agree that preventative healthcare is lacking, partly due to the system and partly due to culture. If the OP had originally said "preventative healthcare" I wouldn't have much to disagree on, but they used a blanket statement implying only the wealthy have access to healthcare in general.
The US also gives free preventative healthcare to many subsets of the population
I suppose all immigrants have similar problems.
[0]: I mean people living in Turkey
Maybe we're more similar than we like to pretend
No it doesn't. Both dosings use two shots, and the "90%" number from the smaller dosing is from an unreliably small sample set of 33 infections -- it could easily be 70-80% by next month when more data comes in.
Can you count infections as a metric of efficacy for a vaccine that's designed to stop infection?
Consider [1]:
"However, protection was 90% in an analysis of around 3,000 people on the trial who were given a half-sized first dose and a full-sized second dose."
AFAIK it's not known how many of those 3,000 in that trial were exposed to potential infection.
The bars are to be calculated using conditional probabilities.
So where did Pfizer's capital come from to shoulder these costs? It didn't come out of thin air, they've accumulated capital from somewhere. If not from taxpayers, someone is subsidizing Pfizer's expenses through Pfizer's revenue stream. Taxpayer subsidies really make sense here seeing how this issue effects everyone.
Companies taking a portion of what they earn from their existing products and investing this money to create new products is beneficial, and we should have more of it.
Additionally, while this is probably not the case for Pfizer, another possibility is that a company can take outside investment to fund development of a new product.
Without those trillions of dollars/euros most probably the capital markets would have been down by at least 50% (my guesstimate, or at least that's where we were headed mid-March), which means that the money available to companies like Pfizer would have been a lot less.
As such, Pfizer saying that they didn't receive federal money is technically correct, but without federal money most probably their market value would have been a lot less right now.
Pfizer's cash situation or ability to spend/pay a dividend has nothing to do with stock price. Pfizer does not have their cash balance invested in other stocks. Ability/willingness to pay a dividend has to do with excess cash.
To the extent there's any relation, it's a high stock price that discourages paying a dividend. If the dividend yield will be basically nothing, why bother spending down precious cash that could be reinvested (because obviously the market values future cash flows a lot more than current ones).
Deflation might encourage a little bit of holding of corporate cash rather than spending it on R&D, sure. But even then I think you're overstating the case.
I think the OP was reflecting on cash flow being used for R&D but your post seems to be more about market capitalization.
But let's look at this more holistically. Pfizer and pharma benefit a reasonable amount from public research. Pfizer has received their fair share of governmental funding in the form of products, services, and research: https://www.usaspending.gov/search/85a918fa6adf5152dbac723d2...
They've also been subsidized by people with illness over the years that isn't related to COVID (directly or through their insurance provider pools). It's in other cases the previously sick that have padded Pfizer's profit margins enough to enable them to accumulate enough capital they could take on this sort of risky R&D. Theres also the costs of enabling laws and defending their IP rights from external pressures the US pushes.
It may not be direct subsidy but there are plenty of indirect subsidies that enabled Pfizer to do this. Let's stop pretending these businesses pull themselves up by their bootstraps to success and take on all the risk: they don't. They very often take low risk returns and transfer to high risk and use subsidized activity (e.g. federally funded research) to their advantage. Anything high risk like pharma is prone to failure and needs assistance.
Should we continue assistance? Absolutely, I think so, it's good for everyone. As one parent mentioned, it is good to see these businesses reinvest in further R&D that lead to new discoveries in therapy and treatment as opposed to simply hoarding capital.
Apparently the thought of the narratives that Pfizer didn't pull themselves up by their bootstraps financially makes some people cranky. Everyone needs assistance (especially in high risk arenas), let's not pretend that assistance doesn't exist simply because its indirect, time delayed, and being shifted around.
A subsidy is, by definition, a governmental funding mechanism. "People with illness" who used Pfizer products in the past aren't subsidizing the COVID vaccine anymore than I subsidize an automobile manufacturer making pickups when I buy my tiny hatchback. It's built into the business model and not really a "subsidy".
I agree with you in terms that we shouldn't view these companies as operating in a vacuum, I just don't think the idea of the markets being propped up is the most congruent way of framing the discussion. Pfizer benefited along with most other publicly traded companies, irrespective of their COVID vaccine.
https://lifescivc.com/2019/12/venturing-a-perspective-on-the...
There are plenty of 50-100M pharma startups; they wouldn’t exist if your number was right.
Isn't there a selection bias in that the startups that got to 50-100M survived because they were lucky with a candidate treatment. The ones that failed were the ones that never found a candidate in time? The difference being that large pharmaceutical companies have to swallow ALL the failures, whereas startups can "just" die.
Not to say that pharma companies don't have some fat that can be trimmed...
How do you account for the failed attempts?
As yomly alludes to, pharma startups exist because they don't own the risk - their investors bought it when they were funded. Big pharma does own the risk.
A company that is spun out from a PhD project in a research group, that has done a lot of the groundwork on grants will need less funding
Same goes for a start-up that for instance make non-invasive assays for diagnosis, since the documentation requirements are lower for such products
Producing something that has to be injected into humans is an entirely different league, since the amount of documentation required for such products is staggering
The cost for marketing will vary significantly depending on your definition of the word, and I suspect that it might be misconstrued as only being "commercials and paid holidays for doctors"
GP said idea to product costs 1B just for r&d. That and 1B amortized over failures (and including marketing) cannot be true at the same time unless there are no failed attempts and unless marketing cost is zero.
I'm also not sure what you would define as a failure. Drug development often starts with several candidates for a target. Over the cause of development the list is trimmed, as candidates show lack of affinity for the target or have side-effects that make them unviable. Would you consider each of the excluded candidates a failure?
I don't get to define that, companies do, but basically it includes everything that does not involve a lab, technician, doctor, nurse, statistician/programmer, etc. The US and the rest of the world are quite different here - if you've ever watched US broadcast in the evening, you'd see TONS of ads for prescription only medicine ("suffering from foo? Ask your doctor about bar"); that's marketing. Taking three hundred cardiologists on an all-expenses-paid 7-day cruise with one 30-minute "purely informative lecture about our new drug" and 7 days of fun? That's marketing too. Lobbying to congress? That's also marketing.
Outside of the US, the marketing budgets are smaller and less overt - but the cruise-style legal bribe-like events are prevalent everywhere.
> Would you consider each of the excluded candidates a failure?
Possibly. You've described one style, but it's not the only one. Many times, it's a weird result from some other research (how Viagra was discovered, how DCA tests were started).
But many things are essentially complete and utter failures - you have a line of research where no viable compound was found at all. BiondVax just failed a 15-year mission trying to develop a universal flu vaccine. Remdesivir is essentially failed even though it is FDA approved (It failed for Ebola; if you look at the data critically, it failed for SARS-COV-2 -- which the WHO's recent studies show even more clearly).
There is some benefit from this research - new techniques, often new devices - but the drug itself is a failure in the sense that it will not generate any income to the company.
Edit: just saw your earlier comment about marketing. It is those things (which you and I mentioned) and a lot more, but it is basically for the company to define in their books and a rule of the thumb would be “an expense a university department developing this to completion without expectation of profit would not have to spend”
Not this year!
This doesn't apply so much to Covid vaccines, as the time frame is accelerated and demand is already high.
There's so many ways to calculate the cost, that I think it's more important to be aware of the assumptions made for the estimate, than the number itself (which I also failed to do in my original answer)
I think people underestimate the cost of drug development, because the numbers are so big, that it doesn't seem realistic for companies to survive
Pfizer’s trial will run for 2 years, so ~$900M for the trial alone. That’s excluding all the work to scale up the production, regulatory filing, distribution, etc.
Edit: my math sucks. $900M, not $90M
I just think big pharma are fundamentally ok with huge cost for trials and are not motivated to decrease it/make it more efficient, since they're ok with their pie being larger. They will just shift costs to healthcare system and will be happy with larger profit.
Now, $10-15k per patient-year is for a typical therapeutic. And that is an average across global trial sites, not just the US. It’s not much money. You go a 15 min doctors appointment and your insurance is billed $150. Now imagine going 1 per week and having multiple tests run each time. Or having to stay in the hospital for a day when the drug is administered. You can burn through $1,000 per month pretty damn quickly.
It doesn't work this way. Pricing of pharmaceuticals is independent of the cost of development. Nobody will pay $200 per Covid vaccine dose just because the cost to develop it went up 10x. Every extra dollar spent on development, is one less dollar of profit.
That's why some drugs never make it to market - the cost to bring them to market and the low price means they'll never be profitable.
Given the amount of work being done by this and other research labs hired Astrazeneca, and comparing this to quotes I've received for a very modest UX usability studies, it's hard to see see this an sort of money grab.
Most basic research is government funded.
It also feels deeply wrong to pull the "but all the research efforts that did not lead anywhere" argument, when Pfizer did not do the research in the first place. They should get compensation for organizing the huge trial, of course; that expertise was why they were on-boarded in the first place. And nobody expects them to manufacture that stuff at loss or cost. But we should not accept public money buying them goose laying golden eggs either.
Oh, and now there are multiple competitors in the market.
The quantity of vaccines needed will make even a $0.50 markup worth billions of dollars every year
I hate to link to a Youtube video, but this doctor walking through the research in the first part of the video is honestly better than any news article I've seen: https://www.youtube.com/watch?v=gFeJ2BqCFY0
I also noted that 40 of the participants were excluded because they had no PCR test done to confirm covid and no antibodies were found in the assay. This is in my opinion a major flaw, as the subjects could have been infected, but had no antibodies left, when the blood sample was taken
Finally seven of the 18 authors declare competing interests, which might have affected the research
Getting back to your post itself, I agree that you can't measure immunity for a longer period than the virus has been around, but that also means you can't say that there will only be a need for one round of vaccines, which was what I was disagreeing with
It might very well turn out, that you gain permanent immunity for a specific strain off the virus, but unfortunately that immunity also introduces selective pressure. Whether the virus is able to mutate in a way that bypass existing antibodies in a subject is obviously still an unknown, but we have seen that it's able to jump to other species like mink, which caused the emergence of the Cluster-5 variant
Since the virus is able to use other species as a reservoir and selective pressure is being introduced, I think it's reasonable to prepare for a scenario, where a vaccine won't be a permanent fix
The society at large is making huge sacrifices and making painful changes to address this collective problem. Are these companies part of "Human society" or not? If they are party of Humanity, then they can make 'adjustments' as much as we are asked to make adjustments.
Still won't be a fraction of the profit that stands to be made from these vaccines.
They then get to recover their R&D expenses and make a smaller but probably decent profit from its production.
It’s easy to complain about Pharma profits when you ignore all the money spent that goes “poof”.
I'd be glad to be shown some examples, otherwise it's "privatize profits, socialize losses".
And if you fold in the start-ups who have one shot and if it doesn’t work out? Plenty of those. They go bankrupt.
Busting the patents on Covid vaccines would be “socializing the gains and privatizing the losses”.
However I'm certain that the category "bankrupt pharma company" is littered with examples.
a) researching Covid-19 vaccines?
b) will they actually get to produce millions and millions of doses?
Almost every case I know of, it's a huge company or even a state owned one.
Who are we actually arguing for/against? The hypothetical "small pharma"?
Keep in mind that just like for banking, due to the amount of (necessary) regulation, there aren't many small pharma companies out there.
But the reasons and ethics of the system being the way it is are separate from the reality of what it is for the purposes of getting things done in the here and now.
For better or worse, as things stand right now, pharmaceutical companies, like other companies, need to make profits - or at the very least avoid crippling losses - in order to survive and continue doing their work.
That includes covering the formidable costs of the many research studies that go nowhere and yield no revenues.
I'm sure you wouldn't find a single person in a pharmaceutical company who would feel good about withholding treatment from any person with a life threatening illness. But what they also have to care about is remaining in business so they can treat and cure many more people with serious illnesses.
Practically speaking, I suppose a hypothetical scenario could be that the:
- the companies are granted patents
- the vaccine lasts for a limited amount of time
- before each patent expiry they companies make minor modifications (say, storage temperature requirement decreased by half a degree)
- the company make "unfair" profits by extending the oligopoly for a very long amount of time
I'm not stating that this will happen, but on the other hand, I find this plausible.
In addition, the aforementioned patents prevent disruption. Even long after the original patent expires.
That is something we want to encourage!
This ensures equitable access, ...you know, that the whole world is actually saved.
In reality, these costs are microscopical compared to the cost of the Covid recession, and all the "stimulus packages" across the planet.
I assume most governments will pay the cost of vaccines, or even pay people to take the shots. The US says it will.
I prefer a system where it's very worthwhile for people to risk a lot and work hard to save my life.
If it was all about altruism, I doubt a vaccine would be developed for many more years.
Money quote from linked article:
"News of the vaccine's success was first made public on April 12, 1955.[7] Salk was immediately hailed as a "miracle worker", and chose to not patent the vaccine or seek any profit from it in order to maximize its global distribution."
But I also know that my grandmother suffered terribly from rheumatoid arthritis, and it destroyed her life. Long after she died, enbrel was developed for profit which was the first really successful treatment for it.
No profits => no treatment => misery.
The organizations who funded the research looked into the viability of a patent and concluded it wouldn't have succeeded.
"the idea of patenting the vaccine had been directly analyzed and the decision was made not to apply for a patent mainly because it would not result in one."[1]
The distinction should also be made that a patent doesn't necessarily affect global distribution. It just gives the rights to license the technology. They could have patented it and then licensed it for free.
[1]https://www.bio.org/blogs/real-reason-why-salk-refused-paten...
It doesn't really scratch at his integrity though, since it was the institution he worked for that raised the issue.
If he was just a brilliant salesman (apart from a brilliant scientist) we never know.
What is beyond dispute is that his discovery saved (arguably) millions of people from a life in misery.
Enter public trading: the opportunity alone for global ransoming will inevitably become the projection that defines the street price for shares and once valuation is up there ransom-level profits would suddenly appear not excessive but appropriate, given the level of paper investments of the latest, valuation-defining round of buyers.
I wish regulating anti-social behaviour out of industry was more popular.
Sounds like you're simply defining a tyrant as someone who runs a profitable company.
I also want to push back on "everything commercially successful is run by tyrants" kind of narrative. I get the frustration, but these blanket, ideological statements do not help anyone, anywhere. Do you make money? I guess you're a tyrant!
Let's not forget, the countries that we put up on a pedestal as the shining examples of how a country should be run (Norway or whatever) are very much capitalistic countries with free markets, IPOs, and commercial companies. I hardly see businesses there characterized as tyrannical.
I do really get the frustration, but it needs to be directed at the failures of our elected representatives. Not, commercial entities.
Companies are unlikely to stay profitable if they’re overly generous. They need to profit handsomely to survive.
Eh, I think that’s kind of old-school thinking.
> Companies are unlikely to stay profitable if they’re overly generous. They need to profit handsomely to survive.
Yep. That’s fine. (Also ignores low-margin industries that rely on volume, but whatever).
If you want a modern society, people have to be able to take risks with their money in order to make more money. Otherwise we can go back to subsistence farming. Do you work? You’re charging a profit. How evil of you! Being a few steps removed from the transaction doesn’t make you any less guilty of profiteering. You’re just as bad as these tyrannical CEOs, the difference is you’re a sucker for building their product while they make money hand over fist.
(I don’t actually believe the last part, but w/e).
I pray anyone of like mind is never in a position to enact such progress-killing madness and fear terribly that government is already full of them.
And besides, it is mind-numbingly complicated to calculate "at-cost" because as others have pointed out, that includes all of the dead-end R&D, ongoing legal exposure, interest on the loans used to cashflow operations at pharmaceutical giants, appropriate licensing of existing intellectual property that these vaccines are built on, and the million other ways money is spent to develop pharmaceuticals.
We all have things (and people) in our lives who are probably a net negative in terms of financial outcome, but we enjoy them anyways because our value systems are more complex than just "maximize profit"
But: this is not a medicine made of a molecule that can be synthesised by the chemical industry. Such a vaccine requires input from the creator and then specialist equipment to manufacture. Poor countries don't have the infrastructure to manufacture and the creator labs are not going to tell you how to produce the vaccine just because you ask them.
In any case, governments should pressure labs to enforce an low prove.
These programs were federally-funded with the goal to produce as much as possible. For production I'm sure that factories were financially compensated for the work.
I'm also sure that you realize the difference between taking a small profit, and the huge margins big pharma companies have.
In addition, the pharma companies have already been compensated with massive grants.
Also, all 3 have made various noises about not making a profit etc, it's quite hard to sort out the marketing from what will actually happen at this point. Oxford/Astra have committed to supplying at least 100M doses to low-income countries for under $3 though.
This vaccine is cheap, 90% efficient and easy to get people vaccinated. The other ones are expensive, 95% efficient and difficult to get people vaccinated.
The Oxford is best only if you either live in a very remote place, or are a very poor place. If you rely on the oxford vaccine it will be a little longer to get herd immunity, but overall your costs will be cheaper.
But I must reemphasize, the above is only about logistics. Because most people live in cities, all vaccines will be distributed in big cities just to get the numbers they need. What ever vaccine you are offered first is the one to take. You personally are unlikely to be offered a choice other than take it or leave it.
Additionally, lots of countries have already preordered all the major candidates, so in those cases its already spent money.
It isn't a new thing for what it's worth. Going back to earlier this year it has been looked at, but we don't really have a clear picture on what will shake out.
We need the vaccine to remove the virus from circulation, not just keep us safe from it as individuals.
Regretfully, it would be not the first example of major economies using the current reality as an excuse/cover to conveniently push political policies/agendas that would otherwise have been impossible to implement (at least not without violating laws/treaties and maybe even basic human rights). I have no intention to fear monger, but I believe way too many are too naive about some of the things that are currently happening. That is, mostly people within those major economies, for people in less fortunate countries already learned the hard way how double-faced those major economies turned out.
How all this will eventually turn out ... anyone's guess is as good as mine. I guess we will all learn, when the immediate emergency of the current situation is over. I would prefer to be/remain optimistic, but thus far there appear to be more reasons for caution and skepticism (at best).
I've read this 3 times and can't figure out what you're trying to say.
Are you saying that rich countries are going to intentionally choose more expensive vaccines, with the intention of suppressing the lower classes?
That's so rediculous. In rich countries (other than the usa) the gov pays for these things not the citizens. Even then, the expensive vaccine is only $40, that's within the means of most poor people.
Not to mention that would screw over the rich people who want to benefit from (vaccine induced) heard immunity.
> .. the gov pays for these things not the citizens .. You do know that the only money governments have, is the money they got from its citizens, right? That is, aside from what they may have earned (though plundered or extorted might be more fitting) from other nations.
> .. the expensive vaccine is only $40, that's within the means of most poor people .. You may want to reevaluate your knowledge about the rest of the world. That is, outside the USA and some the more affluent parts of Europe. Also, that vaccine probably won't cost "just" $40 equally for everyone.
However, believe whatever you want. Time will no doubt teach us all a lessen. Personally, I hope it will teach me that I was wrong with my skepticism.
> Time will no doubt teach us all a lessen.
I doubt it. You need to actually have a position that can be shown to be true or false with the passage of time before you can learn something from the passage of time. You have a bizare, logically disconnected, rant that does not make any predictions. I don't think any course of events would prove you right (or wrong).
> You may want to reevaluate your knowledge about the rest of the world
In context, we were discussing afluent countries, canada europe, etc.
> Also, that vaccine probably won't cost "just" $40 equally for everyone.
They will cost $0 directly. As you say there will be indirect costs based on taxes. However that will be true regardless of if you get the vaccine and be scaled based on your income, so im not sure how you think that applies to your argument sbout class divide.
India's Serum Institute has already partnered to mass produce this vaccine. https://www.ndtv.com/world-news/oxford-says-covid-19-vaccine...
-80C is really close to dry-ice temperatures. So I wonder if its actually -80C or if the researchers were just saying "Dry Ice".
Of course we now have reason to believe that vaccines that don't need dry ice will be approved, so logistics will direct the easier to ship ones to remote places.
Eventually you are right. If the Pfizer vaccine is to be used in remote places the people getting the vaccine will need to schedule it in advance (and probably pay for it) to ensure that once it arrives it is used.
Most of the producers have had their entire capacity bought out in prep for distribution of the vaccine.
Realistically, every major population can be reached in 24 hours by modern transport, and the Pfizer 5000-dose transport package keeps the temperature for 5 days.
You might want to update the comment to avoid confusion.
The other two current candidates are mRNA vaccines, an approach which hasn't been used in humans before -- looks like the harbinger of a revolution but we have no past experience.
This O/AZ uses the actual spike protein embedded in a simian virus (that does not affect humans and has its own DNA removed). It's possible to generate antibodies to the vehicle (virus) which is why a simian virus is used (humans won't already have encountered it) but also means your own immune system could target the vaccine itself. Loewe speculates that this is why the higher dose was less effective.
On the other hand we still have no idea how well these vaccines will work. First, we have (as I discussed) two different approaches in the three current candidates, one of which is fairly new and one which is completely novel. We have had only limited time to see how well they work and have only limited experience in broad efficacy, duration of effect, and, crucially, how long they last (it takes a long time to learn if you'll need a 10 year booster!). We don't know how fast the virus mutates away from the vaccine's target (though we do currently think we have a good idea). And we simply haven't tried enough people to get a good handle on side effects.
One of the difficulties in solving these is that new approaches contain unknown unknown. Look at CRISPR-CAS: got a (deserved) Nobel this year yet may already have been discovered to be ineffective or worse in the real world. That takes time to learn.
Now it's not that the people doing the work are idiots -- they know all these problems better than I do. But I am appalled that this is treated by the press as a distinction between, say, a pair of beta implementations of something, one in Python and one in Ruby.
Going back to systems issues: when we don't know these factors we take a calculated risk (really an estimated risk). The social aspects of vaccination (close to ubiquitous use, the risk of any side effects increasing the anti-vaxx rate for other immunizations, which itself could become a public health disaster etc) mean these factors are upmost in public health officials, not whether they have adequate refrigeration.
Vaccines are particularly difficult for reasons like these above -- there's a reason why they have their own special laws and government-assumed liability insurance. I haven't worked on vaccines, so take this as you will, but I have worked in anti-invectives, have designed preclinical and clinical protocols (including first-in-human) which were submitted and approved by the FDA, run clinical trials, have presented to the FDA and defended protocol design, so I have some idea what's involved and how to read the presented endpoints and findings.
Sorry I’m a total noob in this area.
I answer your question in a parallel comment; click "parent" on your comment and look at my response to jeromegv
Honestly I feel like this vaccine is going to leave the mRNA-based vaccines trailing in its wake in terms of global government adoption.
However for developing world the prices becomes the issue, so you are probably right, this vaccine is cheaper and thus more available.
[1]: https://www.nationalgeographic.com/science/2020/11/moderna-e...
That’s much more accessible to developing / low GDP countries as opposed the cumbersome and expensive storage requirements of the other two.