We have a huge number of interactions with bacteria and viruses and all sorts of microorganisms. Hundreds? Thousands times a day? Scratches in the kitchen while preparing food, for example, floods our body with stuff that white blood cells are required to deal with.
Giving up some of the ability to deal with those for a small reduction in the symptoms associated with a specific disease doesn't seem like a useful trade off.
What we saw was no serious increase in mortality for the immunized, and a significant increase in mortality for the non-immunized.
Seems like the data from that experiment should be taken into consideration when deciding if the tradeoff is worthwhile, right?
https://thehill.com/changing-america/well-being/longevity/58...
Not a research paper, but a good article talking about ADE: https://www.medpagetoday.com/special-reports/exclusives/9164...
Not that it wasn't braindead nonsense for anyone who cared to look at things with clear eyes even when it first came out.
Population level or absolute increases in deaths do not tell you the marginal impact of getting vaccinated. For example, there's no contradiction between both vaccinated and unvaccinated dying more and vaccines being protective.
One would think after a pandemic with an outsized effect on those already in a moribund state that overall deaths would be down, but they aren’t, they are up. Why is that?
Why are excess deaths higher after rollout of the mRNA injections than before?
Nothing about it adds up, other than one sacred cow elephant in the room.
If people are dying more, there is a cause for that, people have tried everything they can that doesn’t involve going down sacred cow avenue, and they’ve come up empty.
I suspect it's your preexisting bias that makes you assume it's vaccines vs any vast number of other possible explanations. The point is, that we don't know what is driving these deaths. Research should be done, and if evidence turns up which suggests it's more likely vaccines than most other possibilities then sure it'd make sense to say vaccines may be the cause. Do you really think we have enough evidence pointing to vaccines being the cause right now? If so, where is it?
Until we have more answers it's impossible to say what the cause is, but what we do know and have evidence for is that Covid has become extremely (and unnecessarily) politicized, that data on the number of cases and deaths have been being interfered with by government officials, that there is a very strong economic incentive to get people to act in ways that could cause them to get infected, and that people who have been careful are growing tired of the restrictions being safe puts on them as well. We absolutely should expect uncertainty in the number of cases and deaths we see reported, and that could result in some amount of increase in excess deaths. So could complications not directly attributed to the virus, but caused by it still.
We've also got a whole lot of people these days drinking poisoned water and people who don't even have drinkable water. I can't even keep track of the all the cities that are under boil water orders. We've got people without power. We've got areas of the country flooding, other areas that on fire, people living in extreme poverty (including those who lost their job due to lockdowns or their ability to work because of long covid or their household income due to illness or deaths).
It seems like if there's one thing we're going to have to start getting used to it's increasing amounts of death. With so many causes throwing their contributions into the mix it's going to take time to sort it all out and we'll have to do it in an environment where at least some of the data is being manipulated and many people have their egos wrapped up in "taking sides".
Personally, I accepted the possibility that the vaccines could have terrible effects down the road (it was clear enough that there were no major issues in the short term) and I came to terms with that ages ago. If it does start to look like the vaccines have done some great harm then at least I can say that the choice to get vaccinated was easily the best that could be made with the information I had at the time. Sometimes you can make the right choice and still end up screwed when new information is discovered. I'm still hoping that doesn't turn out to be the case here, but if it is there's no point in denying it. Pretending it isn't true if it is would only make it harder to try to fix it (if that's even possible).
It should be easy to compare vaccinated to unvaccinated groups to find out if the vaccine is causing problems. But rather then do that, the authorities have done their best to destroy the control group and coerce everyone to take the failed "vaccine".
Unvaccinated people are dying at a much higher rate. If your biggest concern is not dying, you should be vaccinated.
I got lucky in that the 20th medication they tried just before lockdown ended up working. Would most likely probably be dead if things had shut down a month earlier.
Tons of people in support forums were in a panic over lost access. Needed testing / procedure.
Not fun when brain is swelling and doctors say they can’t see you.
When I got Covid. I had to double blood thinner dosage for six month to not have symptoms.
Amazing how similar long Covid and my micro clotting from Factor 5 are.
There's no brushing off this concern, it's vitally important to get this information.
It would be easy to track:
- 2 dose, no other booster
- all boosters
- no vaccine
and readjust results considering age and other bias etc.
If all booster people have excess deaths, than "not from Covid" ? If 2 dose people excess deaths < all boosted people, than something about vaccine? No vaccine could be control.
Considered by whom? The funny thing is that there was no non-covid excess mortality in 2020, that stated on 2021, which is the same time the v{censored} started.
> Unvaccinated people are dying at a much higher rate.
Again, where did you see that?
https://www.documentcloud.org/documents/22275411-group-life-...
Countries like the UK have national vaccination databases. They could easily put this issue to rest with a study of excess deaths by vaccination status, controlling for age/health/etc., except they conspicuously have chosen not to.
https://doh.wa.gov/sites/default/files/2022-02/421-010-Cases...
And here’s the total death rate by vaccination status: https://ourworldindata.org/grapher/united-states-rates-of-co...
I assume you’ll switch to some CDC conspiracy nonsense at this point, in which case we are done here.
Neither is what the GP is talking about.
1. That wasn't a controlled experiment. Observational data < RCTs.
2. You are mixing up mortality and mortality attributed to COVID. It's a common error. For overall mortality the picture is far less clear. For example in the Pfizer trials there were more deaths overall in the vaccinated arm than the unvaccinated arm i.e. RCT evidence = no mortality benefit.
Also, we now have excess deaths above the expected baseline for long periods in 2022, which is unprecedented. Governments are highly reluctant to split these deaths out by vaccine status, but the increase seems mostly attributed to heart and blood clotting related deaths. So the data from the "experiment" is not obviously positive.
There's also the problem of governments playing funny games around deaths and "vaccinated". Someone who died from an adverse reaction immediately following their shot would not count as a vaccinated death, because the _definition_ of "vaccinated" meant you completed the vaccine schedule which was multiple shots over time.
(look under "Am I still considered fully vaccinated if I don't get a booster?")
In trials the vaccines were tested in tens of thousands of people where adverse reactions were meticulously recorded and there just isn’t any evidence that the vaccines caused immediate death in anybody.
Then beyond that there isn’t any evidence that there also is a government conspiracy following the first dubious claim.
> Governments are highly reluctant to split these deaths out by vaccine status, but the increase seems mostly attributed to heart and blood clotting related deaths.
[citation needed]
In the absence of a large enough RCT we're left with observational studies and there are a ton of these now. The observational data shows a large mortality benefit in the vaccinated population and I'm not aware of a single observational study that shows the opposite, but I suppose there could be one out there that I have missed.
The preponderance of the evidence is pretty strongly in favor of the vaccinated population experiencing lower mortality than the unvaccinated population.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8556631/
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8553028/
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8513403/
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8162901/
https://pubmed.ncbi.nlm.nih.gov/35901091/
https://pubmed.ncbi.nlm.nih.gov/35891173/
https://pubmed.ncbi.nlm.nih.gov/35891151/
https://pubmed.ncbi.nlm.nih.gov/35855494/
https://pubmed.ncbi.nlm.nih.gov/35821984/
https://www.covid-datascience.com/ also has some helpful discussions of this stuff if you don't want to have to dig through a bunch of studies.
Yes. It's sound science. What problem do you have?
> It just so happens that the group with the larger number of deaths was the vaccinated group, but we aren't allowed to talk about that. A question: why was this not discussed?
It wasn't discussed because 17 vs 21 in a sample size of 40K is not a statistically significant difference. I don't know how to make that more clear without going into a lesson in high school-level statistics.
What is more ironic to me is that this is the total deaths number, without any regards to cause. And in a large population of 40k healthy individuals, is is expected for a few to unexpectedly die over 6 months. This is ironic, since skeptics also often seem to claim that 10-50% excess all-causes death in the population was just random noise.
This should be obvious, indeed, obvious from high school statistics classes. If the effect does in fact exist and you roll out the vaccine on a global scale, you will end up creating a truly enormous number of deaths that should have never happened. Therefore you must be sure that the number of deaths will reduce. Their data couldn't prove this so it should never have been approved. But of course the whole thing was on rails from the start. The idea that governments would have rejected the vaccine trials when they were telling people vaccines were the only way out of lockdowns and buying up millions of doses before the trials even completed, is naive in the extreme.
The core problem for COVID vaccines is of course that COVID just isn't very deadly and many of the so-called COVID deaths were in people dying anyway of other reasons where the cause of death was spuriously mis-assigned, i.e. not people who will join trials. That's why they struggled to show any impact on death.
https://papers.ssrn.com/sol3/papers.cfm?abstract_id=4072489
[edit: fixed typo in link]
"To examine the possible non-specific effects (NSEs) of the novel COVID-19 vaccines, we reviewed the randomised control trials (RCTs) of mRNA and adenovirus-vector COVID-19 vaccines ... For overall mortality, with 74,193 participants and 61 deaths (mRNA:31; placebo:30), the relative risk (RR) for the two mRNA vaccines compared with placebo was 1.03 (95% CI=0.63-1.71)"
Excess deaths in the UK. Useful because (a) it's all in English and (b) the UK authorities do split out deaths by vaccine status unlike most places:
https://www.telegraph.co.uk/news/2022/08/18/silent-crisis-so...
"For 14 of the past 15 weeks, England and Wales have averaged around 1,000 extra deaths each week, none of which are due to Covid. If the current trajectory continues, the number of non-Covid excess deaths will soon outstrip deaths from the virus this year – and be even more deadly than the omicron wave. The Government has admitted that the majority of the excess deaths appear to be from circulatory issues and diabetes – long-term, chronic conditions that can be fatal without adequate care."
Increases by cause of death:
https://dailysceptic.org/wp-content/uploads/2022/09/image-5....
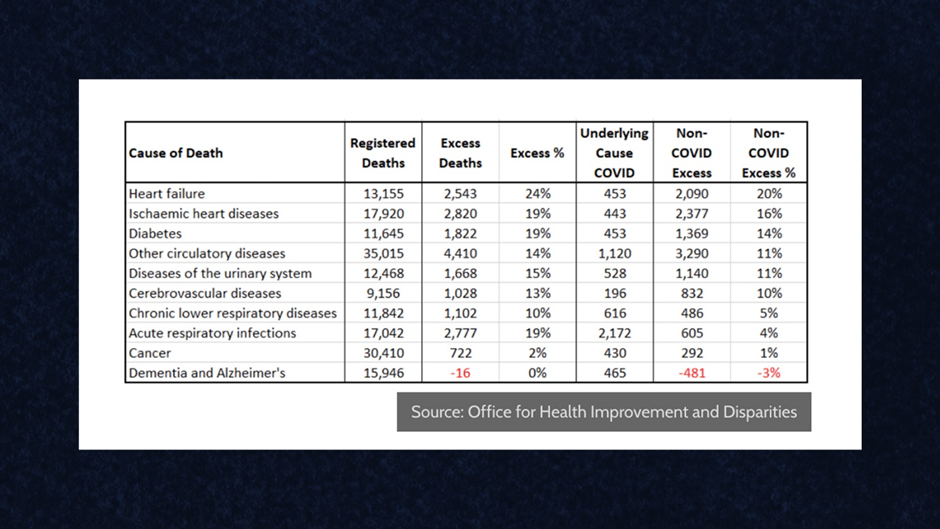
Dashboard that lets you explore the data directly from the source:
https://app.powerbi.com/view?r=eyJrIjoiYmUwNmFhMjYtNGZhYS00N...
UK data at first appears to show that the unvaccinated die at a higher rate. However, this is only because they're using incorrect population figures. Although it may seem absurd the government population figures in the UK are officially labelled "experimental" because they are universally acknowledged to be far too low. In some age groups the official population is lower than the number of people who came forward for immunization, so these figures cannot be used and indeed the UK HSA didn't use the official population stats when computing their own effectiveness rates, but rather estimates from NIMS (National Immunization Service). If the same methodology is used then you can calculate chart 4 on this page from officially released data:
https://bartram.substack.com/p/deaths-by-vaccination-status-...
"The ONS data is interesting because it also includes data on non-Covid deaths by vaccination status ... Using this alternative estimate of the population of England [from NIMS] now suggests that the vaccines substantially increase the risk of death for reasons other than Covid."
Unfortunately and worryingly, even the NIMS estimates are likely to be seriously off. According to NIMS about 9% of the British population refused vaccination but a few months ago the BBC commissioned a professional survey from a polling firm, to ask people questions about their vaccine status and if they didn't take it, why not. They were surprised to discover that 25% of people said they were unvaccinated.
> To examine the possible non-specific effects (NSEs) of the novel COVID-19 vaccines, we reviewed the randomised control trials (RCTs) of mRNA and adenovirus-vector COVID-19 vaccines
31 deaths with mRNA and 30 deaths with placebo with over 74K people in the trial to me means that mRNA carries zero risk. In a sample size that large, 1 additional death means essentially zero correlation.
> https://www.telegraph.co.uk/news/2022/08/18/silent-crisis-so...
Article is subscribe-walled. Not subbing.
> Dailysceptic
I'm not going to accept "Daily Sceptic" as a source.
> PowerBI
I don't find the data in this dashboard to be very incriminating. Excess deaths are still highly attributed to COVID.
> https://bartram.substack.com/p/deaths-by-vaccination-status-...
This article is very painfully committing the Base Rate Fallacy.
See https://twitter.com/sailorrooscout/status/154723580144821043... for a good explanation on that.
You didn't read past the first sentence, did you? Embarrassing, because the article starts by explaining the base rate fallacy and pointing out that the social media meme it starts by highlighting is wrong. Then it goes on to do correct analysis, which shows the conclusions I gave. You'd have known this if you read my post properly too, because I have a whole paragraph about the stats involved in correctly calculating base rates. If you think there are mistakes in the rest of the article please explain them, but you do need to actually read it first.
"I'm not going to accept "Daily Sceptic" as a source."
Again you didn't even click the link and look, did you? The image is a table of data from official government statistics, they simply happen to host the screenshot. But I knew I'd get a response like that from someone. Lack of intellectual curiosity around this topic is extreme - for obvious and understandable reasons of course. But still.
Re: PowerBI
Where do you see that? There are virtually no COVID deaths (a.k.a. "had a positive test a month before death") since the end of the winter in the UK. Look at the data for the various kinds of heart failure, for example. You see clear excess where COVID isn't implicated starting around the end of April.
"1 additional death means essentially zero correlation."
After incorrectly snarking about not understanding statistics, you're now demonstrating a mis-understanding yourself (albeit a very common one).
You can't simply look at a small difference and say "not statistically significant therefore there is no risk". That's not how statistics works. Firstly, the overall sample size was very large, it was an RCT. So we can say with great certainty that the vaccines have no effect on mortality, yet, that was the entire purpose of developing them. I see up thread some people are now trying to deny this, claiming that the vaccine trials were never meant to even study death rates! Truly Orwellian stuff. Death is the endpoint that motivated everything.
What we can't say with great certainty is if the vaccines are truly more deadly than the placebo. But statistical significance is not the same thing as significance. This is a really common logic error you see even amongst scientists themselves (when badly motivated). This result means the vaccines might be more deadly than the placebo or might not, and therefore the correct response is to gather more data. The incorrect answer is to say "eh, yolo, let's assume the optimistic result", especially if you're about to force people to take it on a massive scale.
But of course they didn't gather this data. The people who created and run the COVID vaccine programmes think that any expression of doubt about vaccine safety is immoral anti-science anti-vaxx insanity, which in turn means they can't neutrally measure or act on data. Their conclusions are chosen before they even do a single experiment, so they just went ahead and did it.
At any rate, the placebo in these trials was incorrect. They gave the placebo arm vaccines too, just different ones, so this is actually not comparing against reality (=no vaccine) and therefore overly generous to the vaccine under test.
I also could claim 20,000,000 lives were saved by natural immunity. Or vitamin D from sunshine. Or the placebo effect.
All of those mentioned are also not provable.
You have no idea what you are talking about or how empiricism works. It's laughable.
The best data in the world tells us that 20 million lives were saved. Saying "No it didn't" is not an impressive or persuasive response.
If anyone could, they would have already and wouldn't have to resort to nonsense theoretical computer models.
VERY interested in your attempt though gets out popcorn
https://nitter.ca/AlexBerenson/status/1569648795373166593#m
We are seeing high levels of excess mortality that we shouldn’t be seeing, if the “safe and effective” propaganda was remotely true.
If by “immunized” you mean those who had one or many mRNA injections, then we are seeing high correlation between excess deaths and that population.
And there are many papers detailing likely causal mechanisms between those deaths and those injections.
Sorry people, we were lied to. Was it malice, incompetence, both? Don’t know…
But I see no reason to go on Stockholm syndroming ourselves.
We’re not talking about speculation, we’re talking about clear thinking and rigorous deduction of potential causal pathways. The drop in fertility is, horribly so, blindingly obvious. In country after country, 9 months after mRNA injections rollout for young people we are seeing a striking drop in births. We know there is an effect on women’s reproductive system and men’s. Men’s sperm counts drop a study from Israel has shown. Many, many reports from women of their periods having been effected.
Unfortunately, there is nothing speculative about this. Nobody wants this to be the case. That this was pushed the way it was on young people is criminal and insane.
In terms of death or injury there are definitely cases where it is entirely clear cut just hours or days after an injection somebody is dead or severely debilitated in a way clearly linked to the shot.
Those are deaths or injuries that had no business occurring and yet they did, why?
In the aggregate/macro overview we’re seeing it in data where it can’t be hidden and in the day to day. Just do a search for something like “unexpectedly died”
Again, who wants this thing so many went fanatical about a year ago to have caused this?
Something did cause it though, and at this point the most likely and parsimonious explanation is the shots. And not for lack of trying alternative explanations. Why stick your head in the sand if that leads to more death and destruction. We’ve found ourselves in a hole in terms of societal health, let’s stop digging.
This is the first I’ve heard of the invisible space alien theory. What is the evidence for it?
The US birth rate continues to climb after the introduction of vaccines, for the first time in decades.
I have yet to see a chart that shows a decline that wasn’t painfully manipulate to hide the fact it declined much less after vaccinations than it had in the decade leading up to it. Though I have only seen articles for a handful of countries.
Common internet debate confirmation bias to grab the first thing you think supports your point after a quick scan, link to it like it is a slam dunk, and read no further.
You sounded like you were genuinely interested in learning more, saying you hadn’t seen most of the data so I posted some links to get you started. There is a lot more there than the link you posted.
I don’t think Chudov would say “unfounded,” even if it is temporary that is still a scandal almost beyond words.
“Take this shot you don’t need, that we’ve either terrorized or coerced you into taking and it may permanently or temporarily impinge on your ability to reproduce or cause a host of other maladies “
No part of that is acceptable. And even if it is temporary after one shot, how temporary is it going to be if the shots continue to be pushed and mandated, and each additional shot increases the effect?
The University of California system has just announced they are mandating yet another shot! It is madness and criminal.
Would it change your perspective if you learned that the still birth rate in 2022 was still lower than every previous year, except for the years 2019 and 2020 that he uses as comparison?
https://www.ons.gov.uk/peoplepopulationandcommunity/birthsde...
Does it change your perspective if you learned that the birth rate has been dropping about 2-3% per year, except for the year in comparison (2021) when it was 2% higher than the previous year?
https://www.ons.gov.uk/peoplepopulationandcommunity/birthsde...
Does it change your perspective if you learned that vaccinated mothers appear to have been slightly more likely to have a healthy, normal birth over this same time period (fig 3-9), though the difference was not statistically large?
https://assets.publishing.service.gov.uk/government/uploads/...
All of these links are directly from his blog post, so I know he also had access to this data, which shows it was safe and even beneficial to you to get vaccinated, and he apparently chose to ignore it.
> even if it is temporary after one shot
If it doesn't reoccur though, it is temporary, regardless of what else happens. But the data would already have included the effect of boosters by now. In some ways, the blog post also suffers from a lesser known problem of being too-big of an effect. It was >8% decrease when <20% of the population had a vaccine, so now that >60% has had a vaccine, we should see a >25% drop in births. That is too big an estimated effect he's observing in one specific area for it to be invisible to other statistical measures and countries. So that hints something else is wrong with his analysis, failing to account for something, or taking small numbers as divisors to make them look bigger.
I had heard a fun podcast on excess effect size being a possible yellow-flag for statistics, but cannot locate the exact one for you. If I recall right though, it was related to Andreas Glöckner's discussion of the size of the mental depletion effect linked from https://freakonomics.com/podcast/in-a-job-interview-how-much.... In that article he shows how the correlation was too strong between "mental depletion" and outcome, that it likely points to there not being a causal-link.
Thus, to come back to belltaco's point, his post shows there is far more evidence for invisible space aliens (75% unexplained correlation) who only target Hungarians than for vaccines (25% possible correlation).
Where did you see that?
https://www.scientificamerican.com/article/how-to-compare-co...
https://www.cdc.gov/mmwr/volumes/71/wr/mm7104e2.htm
https://doh.wa.gov/sites/default/files/2022-02/421-010-Cases...
https://www.washingtonpost.com/health/2022/02/08/omicron-dea...
Even granting the unlikely possibility that this mouse model is reflective of the immune response in humans, whatever other microorganisms people were encountering were demonstrably less dangerous than SARS-CoV-2.
Unless you know of some other highly infectious microorganism that rapidly spread to hundreds of millions of people and killed 1-2% of those it infected?
The mouse model is apparently enough for the new booster.
The problem with anti-vaxxers is you just imagine a world in which everything is underhanded and a conspiracy when all the science and data is out there in the open, just ignored.
Senior officials at the FDA resigned over the insufficient evidence of efficacy. Not only was it unclear that they should be approved for seniors, they just opened it up to everyone. It's only gotten worse now. It's not even remotely clear to me that the average healthy person (not on the standard American diet, chronically ill with the typical stuff like diabetes & obesity) needs upwards of 4 vaccines, and counting, for a virus that's much more attenuated & practically everyone has some form of immunity at this point.
Also: to answer your question, from what I can tell the studies haven't shown efficacy. They only show that antibodies rose, which we know isn't absolute proof of efficacy with regards to infection or disease.
Also:
- no good evidence the virus is attenuated (lower hospitalizations/mortality likely driven by increased population immunity)
- a lot of FDA/CDC officials agreed with the decision too, and I think on the whole were proved right to offer to the booster to older populations before all the studies were completed.
- nobody is forcing you to get the 3rd/4th shots, why do you want to prevent other people from getting them if they want them? You are sooo sure they are bad?
Nobody needs vaccines for this. We have actual evidence of doctors who got kickbacks for giving patients addictive drugs they didn't need, of pharmaceutical companies lying about known risks, of scientific papers that are nonsense being published, of the CDC lying to the public because they didn't trust us to act like adults and not stockpile masks. There is a US doctor telling her patients that their illnesses are caused by alien DNA and demon sperm, and she's still allowed to keep her medical license. These are hurting trust in science and public health.
I don't blame people for being skeptical of what's going on, but far too often what people are doing is just putting their trust into whatever backs up what they've already decided must be true. People who thought the vaccines were bad before they had any evidence at all to support that have total faith in every study and doctor they can find which might support their position while insisting that the mountain of evidence that contradicts them is a lie cooked up by a conspiracy.
Everyone should be distrustful of research papers, doctors, and public health agencies right now. They earned that, but that just makes it more important that people do a better job of avoiding their own biases and evaluating the imperfect information we have. For all the problems that exist in science, when the vast majority of scientists are telling us something it's best that we listen. We should be most cautious when listening to people who are telling us what we want to hear.
You are actively attempting to erode trust in public health and then lamenting that people are losing trust in public health. Give me a break.
The mouse models were challenge studies, i.e. how do vaccinated mice respond to exposure to the omicron variant? That's what matters. Versus what you are demagoguing. Conflating with "tested", that since the new booster was given to humans and no abnormal AEs were observed & antibody levels rose, that automatically means it must be effective.
This is precisely the scenario that degrades public trust in institutions when this fast-and-loose science is being rolled-out live on large populations.
However this exact issue you are talking about was debated at the public FDA hearing on whether or not to approve the updated boosters. Most, but not all, of the people on the committee believed that it was worth the risk with incomplete information.
It isn’t ethical or possible to run the studies you want given the existing prevalence in the virus, so you do the best you can. It isn’t fast-and-loose to make decisions with imperfect data when all you have is imperfect data.
Also there were even more interesting and nuanced arguments against the updated booster but evidently you didn’t read the FDA meeting notes and see the arguments from the couple people who voted against it. Oh well.
This is hardly surprising considering two of the people most likely to disagree resigned from the FDA after the last booster approval, due to their disagreement with the process. [0]
The people who resigned were FDA Office of Vaccines Research and Review Director Marion Gruber, Ph.D. and Deputy Director Phillip Krause, M.D.
After resigning, they also published a critique in the Lancet of the policy of boosters for everyone. [1]
[0] https://www.ft.com/content/af8da7d4-43ea-41d6-90ee-f959b3675...
[1] https://www.thelancet.com/journals/lancet/article/PIIS0140-6...
Also those scientists were essentially proved wrong - the booster almost certainly was better for everyone a year ago.
Further boosters is still a bit more complicated but we are doing the best we can.
The facts on the ground changed around July 2021 with the advent of the variants.
and the reasons why it should be clear to you are what, precisely?
Do you have some particular expertise in public health? Or are just another person who believes that applying their own intelligence and internet sleuthing skills are sufficient to allow them to question the decisions made by people who make this sort of thing their life's work?
It’s kind of like a modern engineering failure. It takes multiple failures to bring down complex, redundant systems. That is what happened here.
> when all the science and data is out there in the open, just ignored.
I lost count of the number of times somebody yelled or called me “dangerous” for showing this data. Most of the public data goes directly against the narrative people like to push. It gets tossed right into the “conspiracy” bin. Virtually nothing about our response was based on science or data.
Virtually nothing?
So the thousands and thousands of studies on vaccines, treatments, mask policies, vaccine policies, school policies, air filtration techniques, etc, etc… those were just done for no reason?
To say we live in an imperfect society with imperfect leaders and imperfect citizens is a fair point. Incorrect decisions were and continue to be made for political reasons or religious reasons or whatever else. That’s what happens in an imperfect society. To say “virtually nothing” about the response is based on data is just ridiculous.
Again, anti-vaxxers and conspiracy theorists make up a world where decisions are made in secret for suspicious reasons when generally all the data and arguments are out in the open and are just ignored.
Are all the highly esteemed professors, scientists, politicians, healthcare workers, and researchers who signed the great barrington declaration anti-vaxx conspiracy theorists?
Do you have any idea how many people in real life yelled at me and called me incredibly nasty things for suggesting that maybe, just maybe this myopic fixation on Covid was going to have some serious long term effects and maybe, just maybe we are overreacting?
You can’t speak against the narrative. Speaking out against what we did was and still is career suicide if you are in healthcare, science or research.
There has been a continual incredibly strong push to label anything that goes against “the narrative” as misinformation, “anti-whatever”. Speaking out as a member of the medical/science community gets you blacklisted. Beware of any research that got published in the heat of this mess—there were strong incentives to only publish research that supported “the narrative”.
I don’t support people being shut down as you talk about, however you should also appreciate that a ton of people speaking out against the “narrative” were just grifters spreading misinformation for whatever random reason. A lot of the blame for legitimate dissent being ignored is due to the fact that most dissenting views were actively in bad faith.
Relevant: https://nitter.ca/AlexBerenson/status/1568951911084072960#m
An Example: My friend had undiagnosed alpha gal for months because the anaphylactic reaction happened to him more than 12 hours after eating red meat so they did not know the connection.
Is Long Covid actually not from COVID but from this weekend immune system having to fight off old latent viruses it once had not problem with?
Having a small number data points means that a single outlier can impact your results. And since “no results” typically doesn’t get published, the rare events end up disproportionately represented in journals.
The smaller the sample size, the more likely the “effect” you’re seeing is just random chance.
That's a very small sample size.
Also, it's mice.
Flu was practically wiped out for example. COVID19 was more fit, and many people were taking precautions (ie: masks) that also hampered the spread of Flu.
If mRNA vaccines really inhibited general immune response to other viruses / bacteria, it should be demonstrable. Just line up the number of people who died / got sick of non-COVID19 diseases in 2020 through 2022 and compare them to the COVID19 vaccine patients, stratified for age/sex/race.
There is a simple thing called science. COVID-19 test kits are literally free. It wouldn't even be a hard test to do. EDIT: In fact, most COVID19 test kits come with their documentation, showing how well they test vs the Flu (guess what? Most of them don't detect the flu at all)
See BinaxNow's test kit documentation, page 3: https://www.fda.gov/media/147254/download
> No cross-reactivity or interference was seen with the following microorganisms when tested at the concentration presented in the table below
Meanwhile, Flu type B/Yamagata has gone extinct, proving the point I made earlier.
Be specific. Because each test kit has documentation on how well it has cross-reactivity to other virus strains. I know its complicated with lots of competition here in the USA and lots of different manufacturers.
So I need to know exactly which test kits you were using, and which virus (Influenza type A? H1N1? Adenovirus? Influenza Type C?)
EDIT: For example, Abbot's test kit has the following documentation: https://www.fda.gov/media/136258/download . We can see page 10 how much it cross-reacts with other viruses: which is not at all.
And even then the actual science and data never mattered from a public policy (or even public health) standpoint. It’s been politics, fear-mongering and straight appeals to authority all the way down.
No. My question is if your side has any data at all on the assertions you're making.
Because in my experience, with regards to this debate, one side seems to just be flaunting falsehoods, while the other side has actually done tests and demonstrated their results.
I'm trying to figure out which side you're on. The side with data, or the side without. If you think the data was poor, fine, whatever. Where's your data that supports your viewpoints? Even if you break someone else's argument, it doesn't matter unless you yourself have data that supports your own side.
Outside of vaccines I’ve yet to see any convincing evidence that any of our NPI’s worked in a way that justified their incredible costs on society. The fact that we did them without any understanding of their efficacy is astounding to me.
Can you stay on topic? This subthread is about a simple discussion. Do COVID19 tests detect the flu?
The answer is no.
Now if you wish to move your goalposts. Feel free to do so. But don't expect me to condone or accept your obvious fallacy. If you're changing the subject so intensely, I more or less take it as a discussion win in my favor at this point.
I think I've readily proven that your earlier discussion point has no data behind it. And I have no reason to believe you have data behind any of the other discussion points you're bringing up.
EDIT: Now if you start posting some data, maybe I'll start to listen again. But I'm not going to take or respect just wanton assertions in this subthread.
That is if the authorities were stupid. I can't say for the US but where I live there was no reduction in flu tests and there were still barely any cases found.
If enough people in the population take certain precautions, and those precautions limit the spread of disease, then there is some sweet spot between the virus’ contagiousness and number of people who take precautions that will cause the virus to not spread.
> people with the flu were testing positive for COVID and health authorities were counting flu cases as COVID.
We know this happens, the critical missing part of your argument is your estimate of frequency. If your theory were true, the precipitous drop in flu cases indicates that almost everyone with the flu also had Covid. That doesn't pass the smell test to me - I feel confident we would have heard if there were that high a correlation, given all the research going on at the time.
From my understanding the flu is less contagious than covid so any efforts we were taking to stamp out covid that were holding covid in check would have stamped out the flu.
This is _extremely_ difficult to do, as a mix of both incentive structures and poor policy lead to any death with a positive PCR test being counted as a COVID death.
It's practically impossible now to go back and figure out how many were _actually_ "killed by COVID" vs "died _with_ COVID".
Have you ever read a death certificate?
They don't even read "killed by COVID19". The direct cause of death is _NEVER_ COVID19.
https://dphhs.mt.gov/vitalrecords/certificationofcovid-19
COVID19 doesn't even play a role until 2 or 3 lines later. Doctors write down "Killed by X" which was caused by "Y" which was caused by "Z". COVID19 is never "X", its always Y, Z, or later.
---------
Because we have these statistics, we can correlate "X" causes. If "X" is "blunt force trauma to the head", it is unlikely that "Y" or "Z" will be COVID19.
But don't take my word for it. There's plenty of death certificates, and such data has been coallated together.
https://www.cdc.gov/mmwr/volumes/70/wr/mm7014e2.htm
See Table 2 in this list, as an example. You can see that the immediate cause of death for most COVID19 patients is Pneumonia, unspecified (J18.9), followed by Acute respiratory failure (J96.0).
Which of these ICD codes do you think is being misclassified as a COVID19 death? Please be specific. Any such large scale misclassification would be obviously in the data here.
Why you do the mental gymnastics to pretend this isn’t true is so baffling.
It doesn’t matter anyway. The data required to support our mitigations stopped mattering a long long time ago. ..Sometime back when the “4% kill rate” predicted by the imperial college paper turned out to be very very wrong and when all those temporary military hospital things got closed because they weren’t being used. That might have been a good time to reevaluate what the fuck we were doing but instead of celebrating the fact that Covid wasn’t nearly as bad as predicted we just doubled down for a year and a half more instead.
Honestly it’s best to just take the numbers at face value and assume any overcount is balanced by undercounts.
George Floyd tested positive for COVID19 before he died, but its not listed in his cause of death.
Is that really the best counterexample you've got of an improper death certificate?
https://storage.googleapis.com/afs-prod/media/711012da318e49...
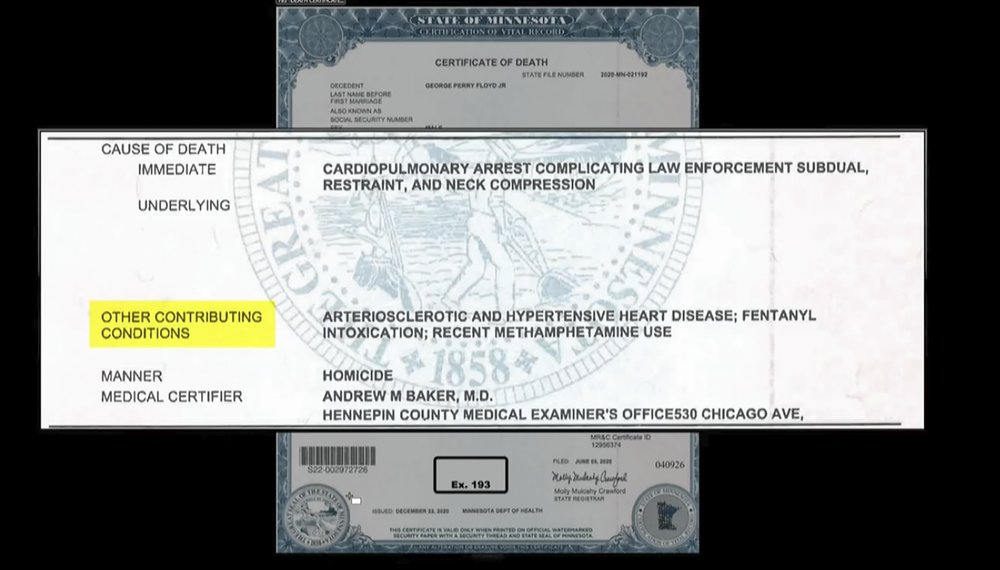
There's not even any COVID19 listed on here.
If 95% of people died from covid, and 5% died with covid, then basically for all intents and purposes and how we use this data, the distinction is irrelevant.
No, it's not. Which is why some health regions are going back and doing exactly this, to reflect the distinction.
Lines up well with my mental model of how the immune system deals with the unknown: a million monkeys not on typewriters but on text editors with copy/paste. Who fire new code, aimlessly mashed up from their library of previous experience, at a test fixture. Any change to unrelated previous experience can increase or decrease their chance of finding something that sticks.
> Two weeks later, the mice were injected in the same area with 2.5 μg of mRNA-LNP coding for PR8 influenza hemagglutinin (HA)
No compromise was posited, it is a consequence not a trade off. Not remotely the same
Out of curiosity, how do you feel about the new bivalent BA4/BA5 booster? It's only been tested on... eight mice [0]:
> So what data specific to the BA.4/BA.5 boosters, did the FDA use to expand the EUAs to include the BA.4/BA.5 boosters? Well, the answer is at least in part very “mice.” Apparently, both Moderna and Pfizer-BioNTech have provided non-human animal data on the BA.4/BA.5 boosters to the FDA to state their case for the EUA. But they haven’t yet shown this data to the rest of the scientific community or the public. This data have reportedly included some preliminary findings from eight mice.
Hey, if that's good enough for emergency use authorization, why aren't the findings in this paper up to snuff?
0: https://www.forbes.com/sites/brucelee/2022/09/12/have-the-ne...
It's highly unlikely the booster trials were on eight mice.
edit: Found the source of the eight mouse thing; it's a misreading of https://www.cdc.gov/vaccines/acip/meetings/downloads/slides-..., page 21. It's not the safety trial, it's the immunogenicity comparison on a small population of older mice previously given the primary vaccine. (The previous slide, #20, has a heading of "Pre-Clinical Studies"; #21 is describing the early studies before the human trials.)
Page six debunks the idea it's only been tested on mice entirely; it cites a trial of 512 human adults for the Moderna BA.4/BA.5 Omicron booster.
> Part H enrolled Aug 10-23, 2022
These people entered the study less than a month ago?
https://www.npr.org/sections/health-shots/2022/08/18/1117778...
As that article notes, flu shots have a similar regulatory regime:
> And some scientists say health officials know enough about how vaccines work to start handling the COVID-19 vaccines like the flu vaccines, which are changed every year to try to match whatever strains are likely to be circulating but aren't routinely tested again every year.
and that the new vaccine still expresses the original proteins the already-approved vaccinations were expressing; in the worst-case scenario that mice and humans react similarly to Alpha/Delta but wildly differently to Omicron/BA.4/BA.5, we're still likely generating the at least the original immune response:
> The new booster will be identical to the original vaccines except it will contain genetic coding for two versions of the protein the virus uses to infect cells — the protein from the original vaccine and proteins from the BA.4 and BA.5 omicron subvariants.
A rapid approval process is going to be important for boosters, for the same reasons it is in flu shots. It's very clear the claim that it was only tested on eight mice is false.
Kinda like how we get a new flu vaccine every year that doesn't go through a years long clinical study
(Edit to fix a typo)
You are anti this vaccine, and your posture is largely fear based rather than scientifically consistent given your not-an-anti-vaxxer self probably gets every year
You see the tautology here, right?
Many years of experience with vaccination gives us useful info on how bodies react to them, which allows us to approve vaccines based on logical criteria.
It is possible to believe the vaccines are safe, and to support their use, while still conceding this point.
Sure, that'd require a time machine. Thus, we're left going "hey, what happened with every other vaccination we've ever done?" and making decisions based on that wealth of information.
People attempting to make this point like to pretend the same isn't true for not getting the vaccine. What's the long-term effect of unvaccinated people getting COVID? Do we have a 20 year safety study on going unvaccinated in this pandemic?
Now you're being disingenuous. There is another approach, and it is the one traditionally endorsed by the medical profession: prudence.
Put plainly: the deontologically correct way of proceeding would have been to say "we don't know enough to assert the vaccines are safe", and not thrust them onto an unwilling public.
>Do we have a 20 year safety study on going unvaccinated in this pandemic?
No. This is why I am not arguing against vaccines. I am arguing against mandates.
> "Well, theory is one thing. Concrete scientific evidence is another. The FDA announcement did mention studies that compared the use of bivalent boosters and monovalent boosters that included approximately 600 and 800 individuals 18 years of age and older for the Moderna ones and 600 participants greater than 55 years of age for the Pfizer-BioNTech ones. These studies reportedly found those who gotten the bivalent boosters had “better” immune response than those who had of those who had received the monovalent boosters. The studies also didn’t show any significant safety concerns with the bivalent boosters, mentioning the usual side effect stuff like pain, redness and swelling at the injection site, fatigue, headache, muscle pain, joint pain, chills, swelling of the lymph nodes in the same arm of the injection, nausea, vomiting, and fever."
Or maybe I wasn't clear in what I said. They have tested bivalent vaccines. Just not for the specific strain of COVID mentioned. I'm saying that seems fine to me since that's what they do for flu, but I'm not an expert. Maybe COVID is different in some fundamental way that means we need to retest for every strain.
It sounds to me as though the tradeoff being made here is: a slightly decreased immune response generally, but a better immune response to the thing you've been immunized against. That seems to be a reasonable tradeoff if there's something really bad going around.
But as they say in the paper summary: more research is needed.
Also: this is purely in mice. They have zero data on whether this is true for humans.