Boy I hope you never need medical care in your life.
(This isn't a free pass to younger people either, they don't vote as much as they should)
Easy enough for someone who thinks they have a “long time horizon” to say.
[1] https://www.wrvo.org/health/2019-09-30/ten-percent-of-all-he...
Those end-of-life patients paid into the system, earlier in their lives, financing the cost of earlier generations of end-of-life patients. It would be unfair to change the social contract now.
In my opinion, it is no different from how adult taxpayers finance public education for children. It is a rolling responsibility from generation to generation.
You may be able to alleviate this financial issue (and not any other ethical issues) by phasing-in this policy change with the youngest generation of Medicare taxpayers, somehow.
> In my opinion, it is no different from how adult taxpayers finance public education for children. It is a rolling responsibility from generation to generation.
This hits upon the core issue: the next generation is substantially smaller than the last and relative costs have ballooned due to greater availability of therapies. The generational contract is that you pay your taxes a percentage of wages -- in effect, a PAYG mechanism. If wages do not rise sufficiently to cover increased costs, that does not imply that the generational contract was unfulfilled; the taxes were paid.
The demographic pyramid and weaker than necessary wage growth really renders the care demanded burdensome to the point where we have already provided elderly cost advantages in insurance in the form of cost premium multiple maximums and medicare from payroll taxes while beggaring the rest of the population in the process.
> In my opinion, it is no different from how adult taxpayers finance public education for children. It is a rolling responsibility from generation to generation.
Fundamentally, children are an investment. They produce cash flow (taxes) from increased public health. The end-of-life are not; by definition, they will be dead soon. It's a horrible thing to say, but in the face of ever increasing elder care burdens and weak public debt/gdp ratios, what real choice is there?
That's an interesting alternative view I had not considered. I think it is debatable. I believed the generational contract to be "healthcare for 65+ with 20% copay, etc., no gov. expense spared" whereas you argue the generational contract to be "Medicare payroll tax of X% is constant over all time; spend it wisely." I would argue the first option was the original intent of the Medicare law.
> Fundamentally, children are an investment. They produce cash flow (taxes) from increased public health. The end-of-life are not
You could argue the same for the end-of-life, in at least two ways: * the end-of-life patient has already produced cash flow to the government, just in reverse order from the student * Good education produces a higher taxpaying adult, the investment you refer to. I would argue the assurance of end-of-life healthcare also produces a higher taxpaying adult.
I acknowledge the costs have gone up faster than wages+population.
I appreciate this view, but it is ahistorical and does not reflect the history of Medicare law.Taken from [1]:
> By the late 1970's, the growing expenditure trends and the changing demographics (an increasing proportion of the U.S. population 65 years of age or over) combined to endanger the solvency of the Medicare Trust Fund. The rapid increases in expenditures for the Medicare program, as well as health care services in general, constrained the ability of the Federal Government to fund other health and social programs. To a certain extent, the growth in expenditures also endangered the Nation's overall economic productivity.
> At the same time as health care expenditures were escalating, some say uncontrollably, the political landscape began to change dramatically. The national mood brought calls for fewer taxes, for reduction of budgets, and for deregulation of market sectors, such as transportation and health. This conviction of less general involvement by Government was reinforced by mounting public pressures surrounding growing budget deficits; Medicare, like other Federal programs, increasingly competed with more global policy objectives. In the space of a few years, the Nation moved from an era when health care was considered a right for all citizens to an era when cost considerations became the dominant issue.
And bear in mind, this was just ~10 years after Medicare was introduced. The nation has always prioritized the future over the past, and has either reduced or restructured benefits to ensure a healthy economy ahead of Medicare.
> You could argue the same for the end-of-life, in at least two ways: * the end-of-life patient has already produced cash flow to the government, just in reverse order from the student * Good education produces a higher taxpaying adult, the investment you refer to. I would argue the assurance of end-of-life healthcare also produces a higher taxpaying adult.
This lacks an understanding of Medicare. Medicare is fundamentally a PAYG mechanism; the trust fund was a short term surplus which is slated to be depleted by 2033 [2]: a mere 8 years from now. Part of this occurs due to poor investment strategy (treasuries only, effectively) but the biggest contributing part of this was the demographic boom. The time for "more cash flow to save for Medicare" isn't today it was 30 years ago. A failure to raise taxes 30 years ago should not constitute an obligation on the youth of today and placing the burden of an excessive tax because of poor demography and unwillingness of prior generations to raise taxes on themselves only harms economic growth at the expense of the elderly.
[1] https://pmc.ncbi.nlm.nih.gov/articles/PMC4195088/#:~:text=By...
One is that US healthcare cost inflation is very high. The average family premium in 1999 was $6k, it is now $27k, for an annual cost increase of 6.1% per year. The long term rate of productivity increase is much lower than that, at only 2.1% per year.
https://www.bls.gov/productivity/images/pfei.png
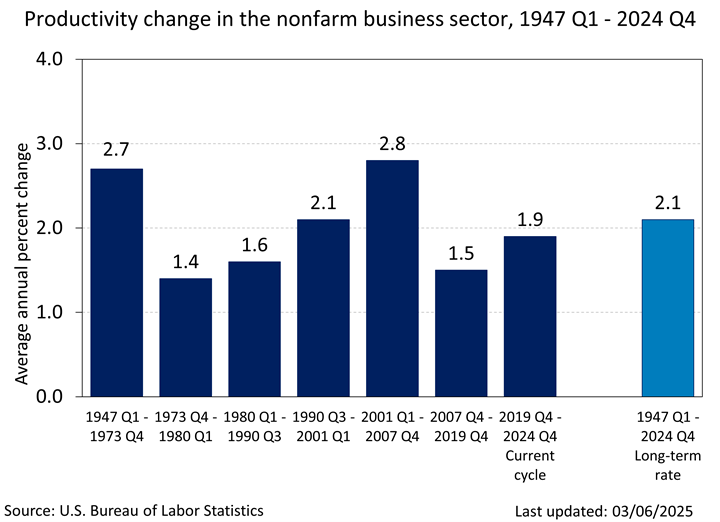
So costs have just risen a lot more than productivity has.
Another reason is that productivity increases aren't evenly distributed. Most productivity growth has been in other sectors, primarily oil+gas and tech i.e. sectors dominated by men who aggressively automate. Healthcare has seen no increase in worker productivity for decades:
https://x.com/DrDiGiorgio/status/1834317735943438835/photo/1
Output is up, but only because of more hours worked. And much of that output is growth of administrative overhead, not actual healthcare as most people perceive it.
Soaring demand + zero productivity growth + cost inflation 3x higher than inflation + no political will to control costs = a death spiral in which the lowest risk decide to go it alone and drop out, leaving ever higher premiums for the rest.
Fundamentally what is the purpose of society if the improvements it makes over time don't improve its's citizens lives? If even with tripling it's economic output it can't care for it's people (just because they are old doesn't make people not part of society)?
This argument is a moral event horizon and the problem should be resolved by other means.
Once one decides to ration healthcare based on estimated remaining QALY, the same logic says we shouldn’t subsidize, e.g., healthcare for people who suffer from cystic fibrosis, or HIV, or aggressive cancers, or. . .
Or if you’d rather, there are millions of children without healthcare in the United states. Would you forgo your access to healthcare for them?
> $365 billion of it went for end-of-life care. [1]
That’s all? Musk alone is worth twice that, and who knows how many QALYs he has left but it can’t be that many. He seems pretty miserable most of the time.
Not everybody gets cystic fibrosis, or HIV, or aggressive cancers. These are a risk. That is fundamentally an insurable risk. However, we will all die. No matter how much money is spent, death comes for us all in old age. Discussing how much is an appropriate cost for end-of-life care when aged is very much a societal question.
> Or if you’d rather, there are millions of children without healthcare in the United states. Would you forgo your access to healthcare for them?
This remains a question, even in Europe. See [1] for a discussion as early as 2000 regarding rationing in the NHS.
> That’s all? Musk alone is worth twice that, and who knows how many QALYs he has left but it can’t be that many. He seems pretty miserable most of the time.
That is a cost each year, and Musk is currently at 244B [2]. We have roughly 20 years of this level of spending or greater. Even if we assumed we could tax Musk 100% (which isn't practically possible because who liquidates his positions), where do you propose to acquire that level of ongoing cashflow? Within 7 years, we would fully exhaust the wealth of the 25 wealthiest American families, even at 100% tax rate. End-of-life care is mind-bogglingly expensive for the United States economy. This either needs to be a tax hike which realistically will it everybody or a benefits cut.
[1]: https://pmc.ncbi.nlm.nih.gov/articles/PMC1173526/
[2]https://en.wikipedia.org/wiki/List_of_wealthiest_Americans_b...
Those are risks. Risks are insurable. However, death is a certainty. It is very reasonable to discuss what we believe society should subsidize for end-of-life care as it will impact everybody, myself included.
> Or if you’d rather, there are millions of children without healthcare in the United states. Would you forgo your access to healthcare for them?
I don't see what pediatrics has to do with end-of-life care in the context we are discussing (Medicare), but I would much rather subsidize pediatrics than elder care.
> That’s all? Musk alone is worth twice that, and who knows how many QALYs he has left but it can’t be that many. He seems pretty miserable most of the time.
Musk is worth 244B [1]. Even if we could tax wealth 100% into cash, we would fully exhaust the wealth of the 25 wealthiest American families within 7 years. These expenses, however, will likely continue for the next ~20 years. We need to discuss benefit cuts or tax hikes on the American population writ large.
[1] https://en.wikipedia.org/wiki/List_of_wealthiest_Americans_b...
You think hospitals aren't full of old people getting care in other countries? And do you think it's possible that young people in the US don't go to the hospital because they can't afford to?
Nobody can ever imagine a better system, even if it’s used in literally every advanced nation in the world. Nope, instead we have to let Grandpa die painfully to keep those stock prices up.
I’m starting to think Capitalism as it’s practiced here is a death cult of some kind.
I would much rather doctors just get paid less. I took my son to the ER. He had a very high fever. They gave him a child's aspirin and me a $700 bill.
I just don't know what the answer is. And really, if you go into a hospital, you get the sense that there's people basically taking advantage of subsidized health insurance providers and patients both. Health insurance in America is absolutely atrocious. Next to gun fanatics, it's the worst thing about this country.
Also the ER is always going to be the most expensive setting to get care.
Why not take him to a pediatrician, if there are no warning signs that he needs immediate attention?
The US system works well if you can pay the bills. It doesn't have the undercapacity issues the UK has, for example. The unique problem is costs. Controlling costs would mean consumers strongly supporting aggressive action by insurers if they take actions to push costs down. What Americans do is the opposite: they stage protests and demand immediate political retaliation on insurers who try to control costs. Then left wing politicians condemn the insurers, and they fold in the face of public pressure. Medical staff know the public acts this way and so bends insurers over the barrel, knowing people will blame the "capitalists" (who have tiny margins) over the frontline doctors and nurses who are actually taking the money.
https://www.vox.com/policy/390031/anthem-blue-cross-blue-shi...
In other countries the public doesn't act this way and costs are more reasonable. Sometimes insurance premiums even fall. Switzerland has a two tier system with basic mandatory health insurance that's basically controlled by the government (private firms provide it but there are price controls and they can't refuse customers). And it has supplementary insurance for higher quality care that's almost free market. This year basic premiums went up 5% and supplemental premiums fell 0.9%
https://www.bfs.admin.ch/bfs/de/home/aktuell/neue-veroeffent...
Cost control requires private sector discipline without people like Kathy Hochul getting involved, but healthcare even in the USA does not have that.
They are on an ACA plan, whereas an 80-year-old would be on medicare. They are also photographed in the article and.... obviously are not 80.
What does the medical expenses of 80-year-olds have to do with the situation described in the article?
Perhaps we could just have a 'poor people incinerator' for those whose expected medical expenses exceed their net worth?
Thanks for putting that out there. Give it 10 years, and I'm thinking we'll see the first "bio-repurposing vats". Never mention crap like that on HN. Too many closet psychopaths looking for a big break.
Understand the attempt at shaming. But there are likely a non-trivial number of readers here with such Methuselan inclinations.
Then you gave the wisdom 'older people use more medical care than younger people'. Like yeah, that is how life/the universe works. My old car requires more maintenance then when it was new. But funny thing about young people, they too will one day be the old person.
I live in red state America, like one of the super red states. The American healthcare system decided it didn't make sense financially for our small community to have ambulance coverage. You know what we in red state America did? We taxed ourselves and have much better ambulance coverage/care then we ever had before.
How we deal with healthcare is a choice.
If you can't afford it on your own, there should just be a palliative care mandate after some age. We shouldn't save the soon-to-be-dead at the expense of the people with a long time horizon.
Or, we should pay doctors far less. I don't think they're multi-millionaires in other countries. Not all of them are in America, but many of them are.