Vaccines are notoriously slow to develop, perfect, and test for safety and efficacy. The original Covid mRNA vaccines were developed at breakneck speeds as far as vaccines go. Unfortunately, much of the funding has since dried up.
In fact, it's HIV that's much harder to develop a vaccine for. HIV vaccine research has been going on for 40 years and hasn't really had any candidates that went beyond "plausible" until recently.
[1] https://www.nature.com/articles/s41423-023-01116-8
[2] https://mrdc.health.mil/index.cfm/media/news_releases/2021/p...
Evolution has driven the virus away from the neutralizing antibodies. This is called immune escape. Recent variants have very little antigenic overlap with the original strain. The original antibodies are not very effective, so people can actually get sick once again.
The FDA now updates the vaccine formulation every year. This means that every year, there is a time window during which the vaccine formulation and the circulating variant are the same. If you get an updated shot as soon as it becomes available, you're immune for all practical purposes until a new variant emerges.
And you’re far from immune with the newest formulations. From the CDC: “People who received the updated COVID-19 vaccine were 54% less likely to get COVID-19 during the four-month period from mid-September 2023 to January 2024.”
https://www.cdc.gov/ncird/whats-new/covid-19-vaccine-effecti...
Even with the original strain/vaccine, effectiveness waned after 6 months.
Regrettably, this is one's on the FDA, as XBB.1.5 was already on the way out when the FDA chose it. Part of the problem was their desire to include Novavax in the lineup. It has a much longer update turnaround time than Moderna and Pfizer, and Novavax had already committed to XBB.1.5 by the time the 2023 VRBPAC meeting took place.
As for the original vaccine, the waning measurements were in terms of antibody titers, not in terms of actual effectiveness against the target variant. Delta emerged in the spring of 2021, and it had significant immune escape from WT (Wuhan.) By the time the population was immunized against WT, Delta had already driven WT out.
There have not been many reported cases of non-immunocompromised people getting infected with the exact same variant they had been vaccinated against or previously infected with, particularly with WT. There has been too much evolution in the timeline to even dig out the signal.
The original WT mRNA effectiveness measurements were 92-95% IIRC. For all we know, the missing 5-8% might be attributable to immune deficits, early infections, and/or incomplete B-cell maturation. I haven't noticed any research that measured the likelihood of single-variant breakthrough infection, but if you find some I'd like to look at it.
As for other diseases, they are not in the pandemic phase, so their vaccines can be optimized accordingly.
I would dispute that "easily evolve" notion, though. There have been billions of Covid cases since 2019, including countless immunocompromised patients who are basically walking virus incubators. Yet there have only been a handful of major saltations. It's actually quite likely that Covid will eventually be defeated completely.
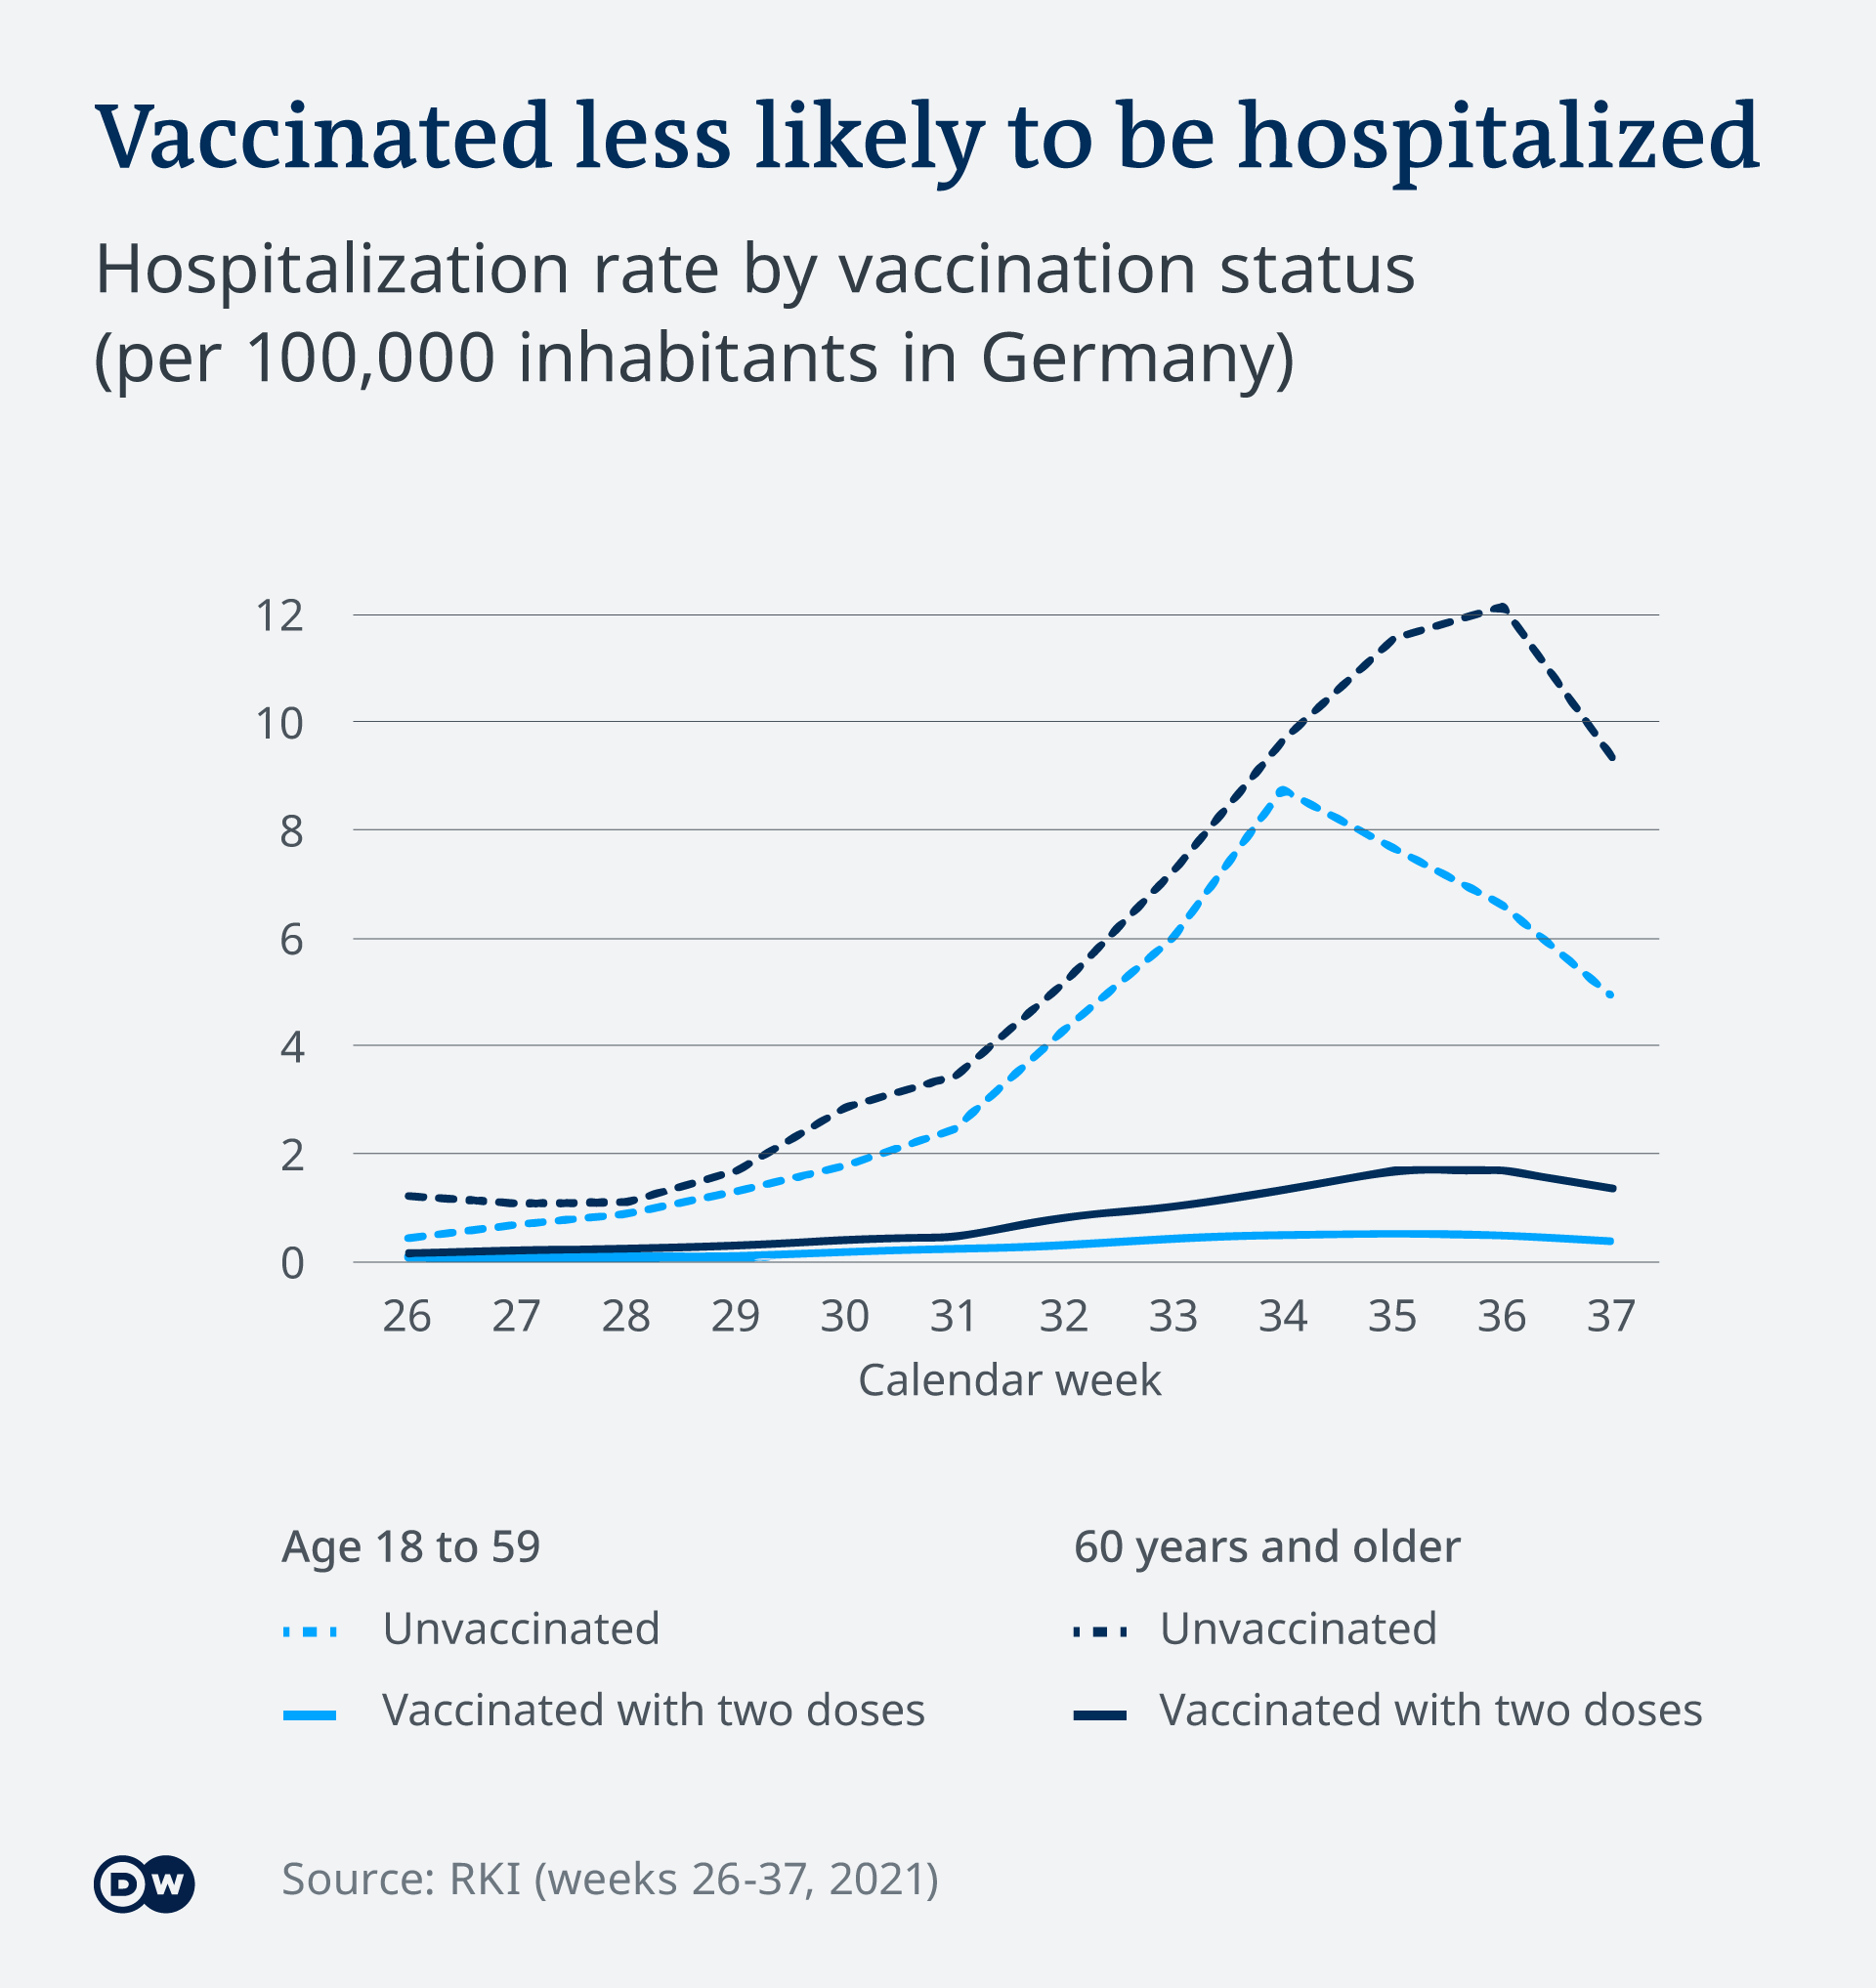
https://static.dw.com/image/59546575_7.png
https://healthnewshub.org/wp-content/uploads/2021/10/CDCcase...
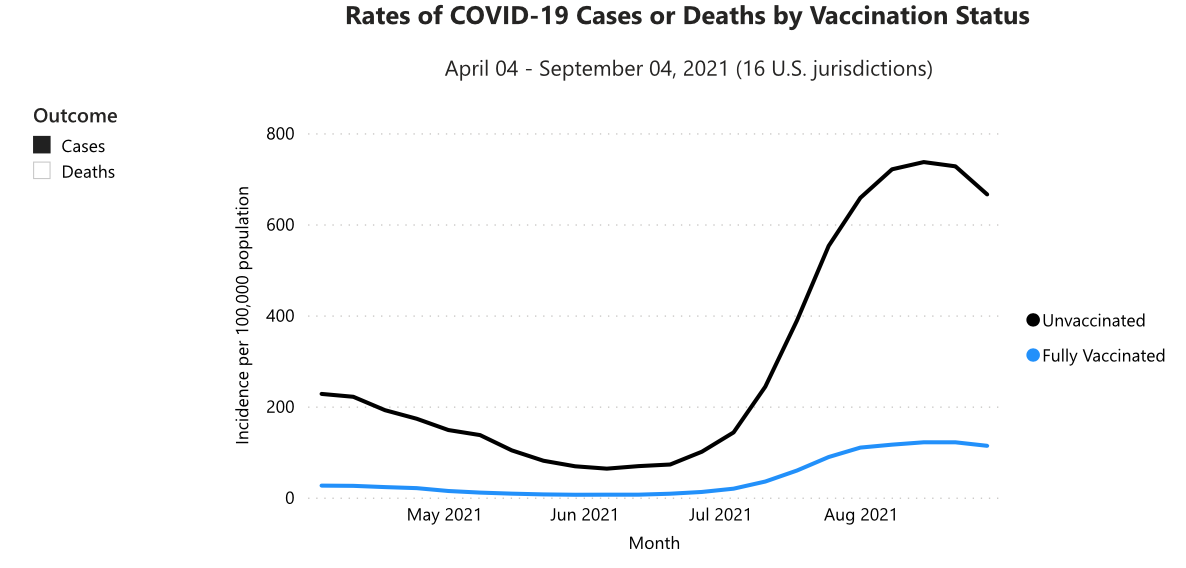
https://arc-anglerfish-washpost-prod-washpost.s3.amazonaws.c...

https://static01.nyt.com/images/2021/10/28/us/virus-breakthr...

https://static01.nyt.com/images/2022/01/10/briefing/11-MORNI...

Since people don't spontaneously recover from HIV infection, and the PrEP drugs have relatively few side-effects, the tradeoff is more favorable.
https://www.pnas.org/doi/10.1073/pnas.2319566121
In case you're wondering, this paper is 100% legit, see e.g. the bio for the big-shot author: https://en.wikipedia.org/wiki/Akiko_Iwasaki
No clue if this easy trick would induce immune escape if a large number of people started using it. I guess it's a good time to get in on the ground floor.
1. "Prophylactic or therapeutic administration of neomycin provided significant protection against upper respiratory infection and lethal disease in a mouse model of COVID-19." 2. "Furthermore, neomycin treatment protected Mx1 congenic mice from upper and lower respiratory infections with a highly virulent strain of influenza A virus. " 3. "In Syrian hamsters, neomycin treatment potently mitigated contact transmission of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2)." 4. "In healthy humans, intranasal application of neomycin-containing Neosporin ointment was well tolerated and effective at inducing ISG expression in the nose in a subset of participants."
The mechanism appears to be that Neosporin triggers an ISG[1] (immune) response? Not a biologist etc, but the results showing that it prevents transmission is only in rodent models, and then showing that a similar biomarker shows up in (some of) the participants and the rodent models. They authors say:
> "These findings suggest that neomycin has the potential to be harnessed as a host-directed antiviral strategy for the prevention and treatment of respiratory viral infections."
[1]
https://classic.clinicaltrials.gov/ct2/show/NCT05449392
Here's Eric Topol's chat with Iwasaki discussing the finding. Topol's blog may well be the best source for Covid research out there:
https://erictopol.substack.com/p/akiko-iwasaki-the-immunolog...
Essentially, yes, neomycin in the nose, if timed perfectly, can activate the innate immune system, but en mass this practice would cause the spread of antibiotic resistance.
Link: https://podcasts.apple.com/us/podcast/this-week-in-virology/...
Besides, we're already spiraling down the resistance chasm with antibacterial soaps, stuffing cattle with antibiotics, overprescribing, and so on.
Obviously it’s not stimulating the immune system but it works as an antiviral barrier. I’ve been using it since I read that study and I’ve avoid 2 of my daughter’s colds since (and still got 3). That might not sound impressive but I have a terrible immune system and haven’t avoided a cold from someone I’ve had close exposure to in as long as I can remember.
That said, I might need to add some Neosporin to my mixture when she comes home with her nose running.
For 150ml of (distilled) water: 1.35g of salt 1.8g of iota carrageenan A drop of polysorbate 20
Heat up the water to close to boiling, add those things, shake it up, and there you go.
Note: That was supposed to be in line with the product that was tested, but I've found adding more water makes it come out of the nose spray bottle thing better. It's still pretty thick, just not a complete gel. Perhaps there's another type of spray bottle that would be better.
That drug is still in use and also highly effective, the new improvement is to provide the same approach with a longer acting injected drug. One reason there has been great interest in this, despite the already effective oral PREP, is that there are thought to be socio-behavior advantages for cases like women in Africa as in this study. For example: the woman does not have to keep a supply of daily pills that a partner can find. Also possibly improved adherence with no missed doses.
The drug itself is not thought to be more biologically effective than the oral drugs, which are basically already at close to 100% effective assuming the patient actually takes them as scheduled.
Higher mutation rate and other shifts vs broadly neutralizing antibodies? Anyways, it would be nice to fully "solve" COVID-19 as it's still wreaking havoc somewhat silently (?)
I also wonder when or if we'll see therapeutic vaccines against either of these and more sooner than later?
Each time I only briefly start staring into the abyss that is "wetware" I'm gladly returning to our comparatively trivial (self-inflicted) complexity in the world of software / computing.