I used to be a close follower of the pharma industry, and you're making it seem like FDA trials happen on molecules and formulations somewhat related to the proposed formulation and then are, like, transitively approved on that hand-wavey basis. This is totally wrong.
For reasons that should be obvious to any engineer that's worked on any kind of even moderately complex system, the molecule that is tested and trialed is the molecule that goes to production.
You don't test "the technology" and then some unrelated other vaccine and then say, there we go, this one's safe.
You test the actual formulation that will go to production. This can't have happened for this yet. The trials are still underway. Unknown risk.
I dunno if you're misinformed or a troll, but that's dangerous stuff to be putting out there.
Vaccines are amazing life-saving tech, and they're safe because of our cultural technologies (FDA trials for e.g.) that make them safe. You can't take all the safety gear out and still get the same safety rating. Doesn't make sense, lol.
In some areas of medicine we can afford to move slowly and we absolutely should - but when it comes to the flu we don't have that luxury.
But there are many parts of this vaccine that is shared with previous ones and the mechanics have been tested thoroughly. The science is the same. There's just no credible reason for those with normal immune systems to delay.
"This can't have happened for this yet. The trials are still underway. Unknown risk."
That's just simply untrue. The trials completed. Read the link.
Please stop spreading misinformation during a deadly pandemic.
Moderna's FDA trial: https://clinicaltrials.gov/ct2/show/NCT04470427 Estimated Study Completion Date: October 27, 2022
Pfizer's FDA trial: https://clinicaltrials.gov/ct2/show/NCT04368728 Estimated Study Completion Date: May 2, 2023
JnJ's FDA trial: https://clinicaltrials.gov/ct2/show/NCT04505722 Estimated Study Completion Date: January 2, 2023
You are saying that I am putting people, or society, at risk simply by stating the simple, 100% true fact that these vaccines are not through FDA Phase 3 trials.
The implication of this is you believe it is best if people are NOT given informed consent, that they are kept in the dark, and told lies about the status of these vaccines, because doing so will encourage more people to take them.
I'm sorry, man, but that is just awful, terrible stuff.
Coursera has a course on bioethics, you may want to inform yourself before you engage in discussions about medicine, because you are totally operating in an evil way.
I just think you're taking issue with silly things, overblowing the risks and trying to make other people scared. That's seriously messed up.
Be truthful. You've decided not to take it no matter what. Now you're back-filling reasons not to. If you truly were about your ethics, you'd stop trying to make others afraid because you are.
I have said zero about the safety of the vaccines. I have only stated the unassailable fact that they have not completed phase 3 trials.
How is telling the facts about the status of the vaccines spreading doubt?
I have taken plenty more vaccines than you, I'm sure, I'm not some anti-vaccine nutcase. I love medical technology, I love vaccines. I also love bioethics. I wish more people, like you, did too.
You say I'm afraid, and you couldn't be further from the truth. I'm more well-informed about covid than most people I interact with on a daily basis, and I live in a state that values individual autonomy, so we've experienced basically zero impact on our daily lives because of covid. Some folks used to wear masks, most folks didn't. Everything remained open, save a brief closure of our bowling alley, now thankfully back open.
I walk around without any fear whatsoever and all my local fellows seem to as well. Nobody talks about covid or really cares much about it all. Very few are vaccinated.
Life is fine.
Others are more scared. Others, like you, are trying to hide information about the vaccines. That sucks.
I hope your life improves, friend!
You know nothing about me.
Strange you think we should all be as subservient as you were when you were a Marine. I mean, I get it, I want our armed forces to have a solid CoC that can be relied upon, but pushing it to the point where you have to obey orders to take random needles without any informed consent seems a bridge too far for me. Stranger still is you seem to think this is how we should operate in the civilian world.
The vaccines are safe.
There are lots of things we do see and we should worry about. The problem is that we can't tell right away if it's just noise, if it's a potentially rare side-effect. Then you have the problems like Myocarditis, which are clearly caused by the vaccine, which we hand-wave away with speculative "the benefits still outweigh the risk" scenarios:
https://cdn.arstechnica.net/wp-content/uploads/2021/06/Scree...
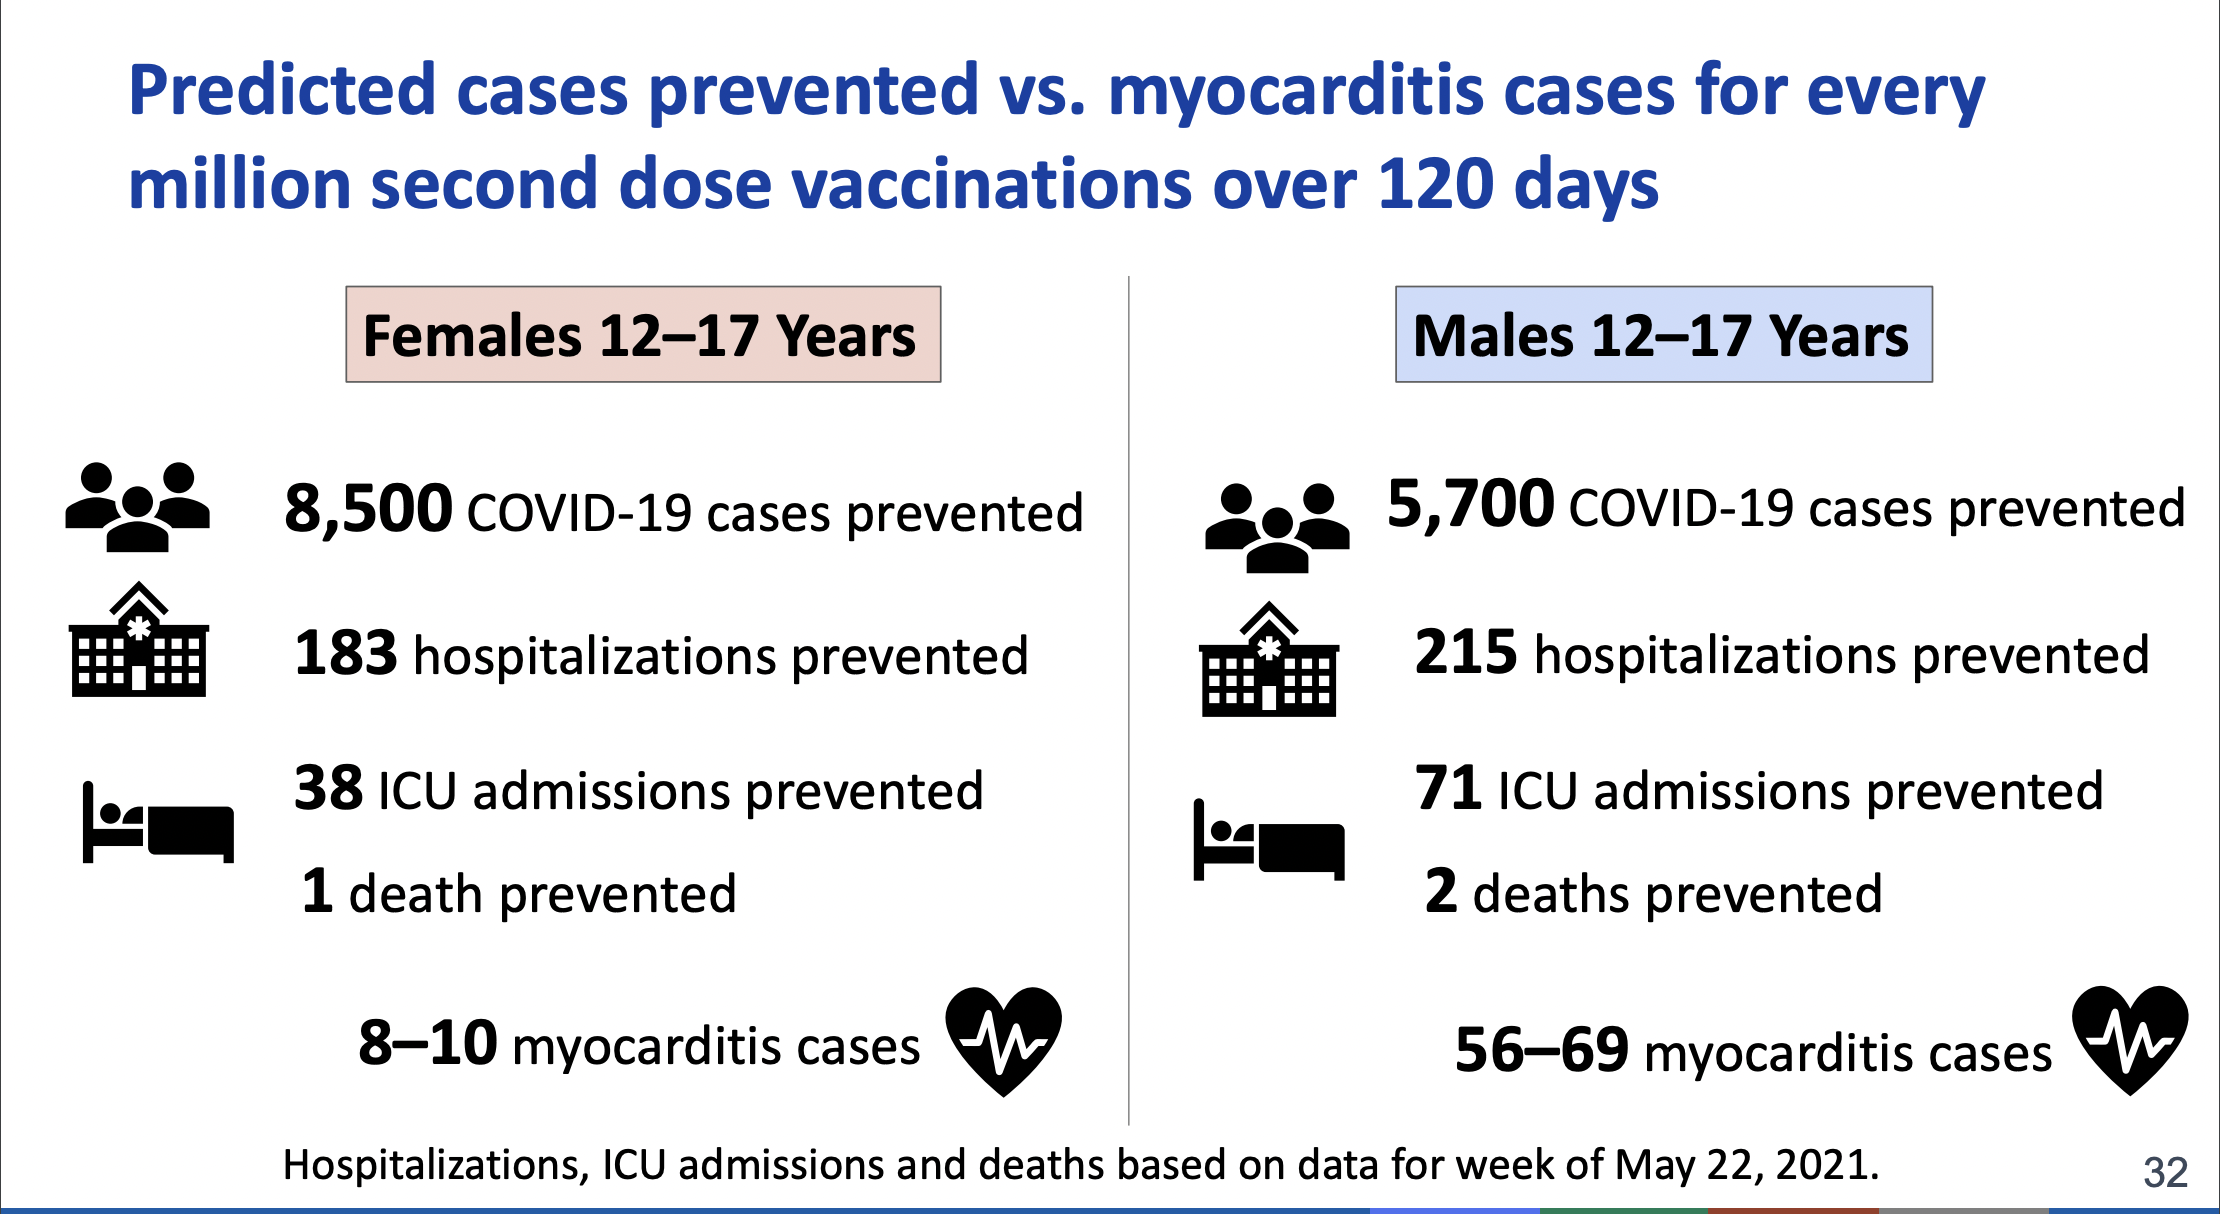
this is not handwaving, this is the foundation stone of modern medicine.
Speculative scenarios based on predictive factors that you could just fudge until the result looks "right" to you, those are the essentially quackery.
We have now had two separate rare-but-serious side effects of different Covid vaccines: the CVT issue with J&J, and the myocarditis issue with the mRNA vaccines in children. It's disingenuous to suggest that the vaccines are "safe" merely because they've been widely administered; even the question of what "safe" means is a far more nuanced question than you're presenting. For children, in particular, two-dose vaccination with the mRNA vaccines is probably a poor risk/benefit profile. We didn't know that until we started dosing enough kids to see the rare side effects.
The phase 3 trials were not powered to detect rare side effects, which is part of the reason that they're still classified as emergency use, and not fully approved.
I am an advocate for vaccination, but it's not right to ignore these issues.
Safe is always relative. If you don't think the vaccines are safe enough, then please also be consistent and don't engage in equally unsafe activities, e.g. don't drive a car, exercise regularly, eat healthily, don't encourage your girlfriend/wife/daughter/friend to take the contraceptive pill or, even worse, get pregnant, also do not take a large number of other drugs etc.
Again, from what we know today, it is safer to vaccinate your kids then driving them around in a car. Even when the risk/benefit profile is even/negative, absolute risk is super low.
...and if it were choice between vaccinating kids and driving them places, then this example would be relevant.
We don't approve drugs simply because they're less risky for a target population than some other selection of risky things.
> Even when the risk/benefit profile is even/negative, absolute risk is super low.
Yes. So is the benefit.
These vaccines are very, very unlikely to give anyone a hard time. Nothing's without risk, but even for the unlucky that doesn't even sound that bad.
As soon as my son is eligible, he's getting it, too.
The chances that a child will experience anything other than extremely minor illness from Covid is also very rare. The current numbers are teetering on the edge of implying that children are at more risk from the vaccine than from the virus.
My definition of the word "safe" includes the rational weighing of risks vs. benefit for a target population. Is it worth it to put kids at risk from myocarditis that exceeds their risk from Covid, just to reduce population-level Covid stats and reduce the marginal risk to the elderly? I don't know, but it's not a question to simply ignore.
Child deaths attributed to vaccines [2]: 0. We can break this down further: 3 deaths from blood clots attributed to adenovirus vector vaccine, none in children. 616 reports of myocarditis[3], 393 confirmed, none fatal.
[1]: https://downloads.aap.org/AAP/PDF/AAP%20and%20CHA%20-%20Chil...
[2]: https://covid-101.org/science/how-many-people-have-died-from...
[3]: https://www.cdc.gov/coronavirus/2019-ncov/vaccines/safety/ad...
Moreover, you're implicitly using a biased selection of data to make this argument. Want more children to die of myocarditis? Keep doing the same thing we're doing now. It will happen. We've been vaccinating kids for a fraction of the time they've been getting Covid.
I will say this for the benefit of others: regarding the CDCs numbers, in particular, they've used the incorrect counter-factual (no doses vs. two doses), and substantially mis-represented the rates of myocarditis in children.
https://medium.com/@wpegden/weighing-myocarditis-cases-acip-...
I've been mortified to see the CDC spreading this kind of mis-calculation so widely. It's simply unconscionable.
This is true by medicinal standards, but it's also a sleight-of-hand. The AstraZeneca vaccine had a rare side-effect that was right on track to kill more young women in Europe than the virus itself. That's why it was banned. By that standard, I could argue the viral infection is also safe - for young women at least.
1. https://www.ema.europa.eu/en/news/covid-19-vaccine-astrazene...
It isn't false, though the blanket "it was banned" statement lacks context:
https://en.wikipedia.org/wiki/Oxford%E2%80%93AstraZeneca_COV...
> It is generally advisable to get Moderna/Pfizer if they're available and you're a young woman but the chance of mortal thrombosis is around 5 per one million.
No, the risk for anyone to develop a lethal thrombosis is roughly 5 per million. The chances are much higher for younger women, to the point where it exceeds the risk to die of COVID.
It's not even close, for women age 20-29 the risk of fatal thrombosis is 1:250k, while Covid is somewhere around 1:25k [1]. That's a whole order of magnitude.
The risk/benefit ratio of AZ vaccine is only poor when the risk of exposure is very low [2].
[1] https://www.nature.com/articles/s41586-020-2918-0/figures/2
[2] https://assets.publishing.service.gov.uk/government/uploads/...
I have yet to find a source that gives the risk for that cohort.
> ...while Covid is somewhere around 1:25k
Even if it's an order of magnitude higher, the risk of a actually getting a PCR-confirmed infection is an order of magnitude lower.
Again, Germany: 28 deaths of women in that age group over the course of the pandemic[1], including all potential co-morbidities that may tilt the risk in favor of vaccination.
> The risk/benefit ratio of AZ vaccine is only poor when the risk of exposure is very low.
This is comparing "ICU admissions" against "Serious harms due to the vaccine". Utter nonsense. Why not compare mortality? Probably because it wouldn't look too good...
[1] https://www.statista.com/statistics/1105512/coronavirus-covi...
The data is publicly available for many countries, e.g. here for the UK:
[1] Report on adverse reactions until 16 Jun 2021 https://www.gov.uk/government/publications/coronavirus-covid...
[2] Vaccination statistics https://www.england.nhs.uk/statistics/statistical-work-areas...
Check the table with reports and fatalities by age, and the paragraph interpreting the data. Together with [2] you can calculate the fatality rate for the 20-29 group. In the end you'll end up with a fatality rate for women age 20-19 in the range of 1:150k-300k (quick back of the envelope calculation).
> Even if it's an order of magnitude higher, the risk of a actually getting a PCR-confirmed infection is an order of magnitude lower.
The source I posted is a metastudy, computing IFR based on seroprevalence from many different countries, so PCR tests have nothing to do with it.
I really can't, because there is no information on which age group got which vaccine. The AstraZeneca vaccine has been restricted in the UK for under-30-year-olds as early as April.
Here is a study (Italy) that estimates the risk-reward ratio (fatalities caused vs. prevented) is unfavorable for the entire below-30 age group, including males:
https://www.medrxiv.org/content/10.1101/2021.05.07.21256826v...
> The source I posted is a metastudy, computing IFR based on seroprevalence from many different countries, so PCR tests have nothing to do with it.
This is true, but PCR tests is how we count actual infections and deaths. When calculating the risk of getting infected, IFR alone doesn't help me, I need PCR tests as a metric of how many infections are actually occuring.
Alternatively, I could use seroprevalence: Assuming that seroprevalence is 10% (way higher than in your somewhat outdated source), then over the course of the pandemic, assuming IFR in our cohort is 1:25K, then the absolute risk was 1:250K - roughly on par with the "vaccine fatality" scenario. This is just an example to show that the numbers aren't clearly in favor of the vaccine.
The vaccines (being administered now) are safe.
Yes, if it was a wide-spread problem. The side-effect that killed AstraZeneca wasn't widespread, it was extremely rare, and it was caught because it was such an unlikely combination of symptoms. Yet, this extremely rare side-effect was enough to make the vaccine more dangerous than the virus - to young women at least.
In a year, when all the facts are collected and processed, we'll see how much trouble the Pfizer vaccine really caused in terms of Myocarditis. Then we'll scramble to make up numbers on how many infections must've been prevented by the vaccine to make it all worthwhile.
...like COVID in young people?
It's true that Myocarditis often goes unnoticed and undiagnosed. That's what makes it dangerous. It's a leading cause of cardiac arrest in young people. If you actually do get diagnosed with Myocarditis, it's not necessarily a mild case. That's what makes me suspect the cases being reported now are just the tip of the ice berg.
We do already have long-term data. You would see side effects for a vaccine within six months, and we have been administering it for much longer than that.
The vaccines are safe.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7956899/