You've made a simple logical error: a study claiming that people who have goals can fend off depression does not imply that those with depression have it because they do not have goals. It means that some people who don't have goals, but do have depression, may remedy it by getting goals. But not everyone.
If the research above is resulting in psychiatrists becoming lazy, it's because they're making the same logical error you are making. So in that sense, you should avoid doing so, since the kind of error you are making is the very thing which leads to the behavior you've experienced.
The proper response (by you, and psychiatrists) is to conclude that trying to encourage goal formation in those with depression seems wise, and will help some, but many (like yourself) will not benefit. Nor should we invert causation and assume the reason people have depression is due to lack of goals, much like if we determined that eating a specific kind of food helped prevent cancer meant that those who for whatever reason didn't have that food in their diet were somehow causing their own cancer by neglecting to eat it.
It really doesn't show this at all, you are misreading the study because the author of the article misrepresents it. Very few correlation studies turn into causation studies. Even when we have entire subfields dedicated to it. See amyloid beta.
Other possibilities "goals are protective against anxiety and depression but not changeable" "other factors increase goal driven behavior and protect against anxiety and depression" "goal driven behavior is protective but not curative of anxiety and depression" "goal driven behavior increases likelihood that individual gets treated for anxiety or depression"
Any of which would mean that increasing goal driven behavior would not help with anxiety or depression.
> We wanted to understand what specific coping strategies would be helpful in reducing rates of depression, anxiety and panic attacks.
> Our findings suggest that people can improve their mental health by raising or maintaining high levels of tenacity, resilience and optimism,” she said. “Aspiring toward personal and career goals can make people feel like their lives have meaning. On the other hand, disengaging from striving toward those aims or having a cynical attitude can have high mental health costs.”
The second quote is really not far from presenting lack of perseverence or negativity as an active choice, putting the onus on the patient.
The first is that because something is on average true does not mean it is always true. There are cases where perseverance does not help depression. There are many where it does. On average it helps, which is the claim.
Next, it it is not fair to presume that because something helps, that it has a causal relationship with that thing. Most people feel less depressed (temporarily) if they take a dopamine agonist. This does not necessarily mean that their depression was caused by a lack of dopamine, only that dopamine helps. In the same way, focusing on goals will help a lot of depressed people. Influence does not imply causality.
And the last part of that statement about disengaging from goals and having a cynical attitude are also facts not conjecture. Negative thinking and disengaging from goal pursuit are linked to mood decline in virtually all people. This does not imply that people have full control over their thinking and goal pursuit or even that there aren't some people for whom such control is next to impossible.
As clinicians, we teach clients to work with what they have and make decisions that will help them. This study outlines some things that are typically helpful. It does not say that they will be helpful or possible for everyone.
I think what trips me is that the article is not expliciting these caveats either. I fail to find a good analogy, perhaps it would be like explaining how sitting around is bad for your health to an audience including wheelchair users.
Sure, it wouldn’t be a false statement, but you’d try to address the elephant in the room somehow. I just wish people don’t get weird advice ideas for depressed people in their life reading the post.
Agreed, but what do you do if it does not help them. THAT is the problem.
From the study: "People who showed more goal persistence and optimism during the first assessment in the mid-1990s had greater reductions in depression, anxiety and panic disorders across the 18 years, according to the authors.
And throughout those years, people who began with fewer mental health problems showed more increased perseverance toward life goals and were better at focusing on the positive side of unfortunate events, said Zainal."
and they conclude with your inverted causation:
"Our findings suggest that people can improve their mental health by raising or maintaining high levels of tenacity, resilience and optimism,” she said. “Aspiring toward personal and career goals can make people feel like their lives have meaning. On the other hand, disengaging from striving toward those aims or having a cynical attitude can have high mental health costs.”
So people who are not depressed do not easily get depressed. Really? That is the ground breaking work? Re read that part, again and again, and tell me where my logic is wrong. They are saying correlation is causal.
If they said a heating pad could help me fix my muscle strain, does that mean they are saying that I caused a muscle strain by not using a heating pad? That's absurd of course.
They are saying that focusing on achievement of life goals (as opposed to focusing on "fixing" yourself) can have therapeutic value.
>If they said a heating pad could help me fix my muscle strain, does that mean they are saying that I caused a muscle strain by not using a heating pad? That's absurd of course.
If you look at the rest of this thread that is how everyone is interpreting it. read them and talk to them. I am not doing that, doctors do it.
I just told you they were wrong about me during my 30 years of treatment. They thought I had a mood disorder but I had a metabolic disorder. so in this case, yes, they knew less than I did.
I have PARTIAL GCH1 deficiency. This affects a lot more people since it is not detected at birth.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2679294/
And I am in no way blaming all mood disorders on this gene change.
To me it looks like most of them lack professional curiosity and certainly basic empathy. I lost all my respect for doctors over the 6 years based on how I have been treated.
I don't see this as blaming myself, it's just how the brain works. Chronic stress has negative effects for all mammals. Take a look at forced swimming, visible burrow, or other stress experiments. It isn't the animal's fault that it has a negative reaction (in terms of cortisol, neurotransmitters, depression, anxiety, mental/physical fatigue, or whatever) to the stressful situation. The brain has evolved to generate these responses to stress, presumably as a survival tool to help prevent the even worse effects of chronic long-term stress. The one advantage we have as humans is that we have a certain amount of control in getting out of stressful situations.
And I agree, even when my tests came back weird my primary care doctor would say, "What do you want to do now?"
Argh
It is frankly absurd to put this onto the patient. It is all about their perceived Physchological basis of the disease, they will humour you on tests and some low harm drugs until you run out of stuff and hope you will finally see the light that CBT will help you.
I have done much of the foot work on ME/CFS. Start looking into aldehydes (malondialdehyde specifically) and the role they play. Also, if you can get your genetics from Ancestry it could help you understand yourself more.
We have far too few doctors per capita to have enough time to treat people. This is mostly because we have institutions set up that reduce the number of doctors that are output (e.g. we have about the same number of medical schools as 100 years ago).
tl;dr doctors have no time, there are lots of knock on effects to this.
more doctors, less income though...
This is the thing I hate most about dealing with doctors. As a child doctors failed to diagnose in me a condition so obvious that a friend of my mother, who works at an airport, was able to figure it out from a mere description. Still my mother had to get angry with the doctor before he would perform a simple blood test for it!
Like in any profession, most of them suck at their job. That wouldn't be such a big deal except that the system in the US is set up to make it absurdly difficult and ludicrously expensive to shop around.
However, it seems that some physicians oversimplify diagnosis so that _only_ the likeliest scenarios are considered. It's also an opportunity for subjective biases to influence an individual doctors definition of "likely."
E.g. Trans broken-arm syndrome
I "only" had a bad situational depression but when I was at the bottom it was clear that nothing normal, pep talk etc was connected to my reality. And even long after that it was infuriating to be talked down by people with 'lazy' innuendos.
Yet ... I myself realize that in my brain there's a little 'will' part that you can focus on which kinda resonnated with the self part of depression and how you may (in time) give it a push to move away from the depressive state faster.
Sorry if it annoys you, I'm mostly trying to share my experience. Do the best you can in you context. Best wishes.
I feel this. I hate all of these phrases.
"Just get a hobby","Go outside more","Set better goals","Pray more","Eat Better","Just adjust your mindset","Just work harder","Make your bed","Read a book","Try meditation","Take a nap","Drink more water","Doubt your doubt", and on, and on, and on, and on, and on, and on, ...
/rant
This is for me a (as a fellow sufferer of some of these conditions, who has never received any state support and doesn't even have health insurance) an extremely shaky moral ground.
Because 95% of the homeless population and drug addicts are clinically diagnosable of most of these conditions under DSM IV definitions. And almost none of them receive anything.
If you are homeless and do not have an address there is zero chance to get disability. That is why we should house them first without any qualifications. Or maybe they justneed to set better goals. :)
There is only wealth in this country because we treat the most vulnerable like garbage.
I think it's more likely that if you're not depressed, chronically anxious or having panic attacks, you'll find it far easier to muster some perseverance.
“Our findings suggest that people can improve their mental health by raising or maintaining high levels of tenacity, resilience and optimism,” she said. “Aspiring toward personal and career goals can make people feel like their lives have meaning. On the other hand, disengaging from striving toward those aims or having a cynical attitude can have high mental health costs.”
"Greater within-subject increased goal persistence (but not positive reappraisal or self-mastery) led to larger future declines in disorder counts. However, within-subject change in disorder counts did not substantially influence future change in each cognitive or behavioral strategy"
Participants were 3,294 community-dwelling adults ages 45.62 years
I think that's a problem with the influence of psychology within psychiatry? There is little ability to distinguish organic disorders and the endogenous vs. exogenous question only really gets resolved with respect to whole diagnoses, less common to distinguish w.r.t. an individual.
Perhaps everybody struggling with anything has a yet-unknown condition that could be treated with drugs.
Yet based on how we act, even with a handicap, our outcomes will vary widely.
Curious, were these medications for the symptoms you mentioned in general (Depression, Anxiety, Panic Disorders), or specific to the genetic disorder that caused those symptoms?
(I assume the latter, but I hate to assume.)
https://en.wikipedia.org/wiki/Tetrahydrobiopterin_deficiency...
https://jamanetwork.com/journals/jamaneurology/fullarticle/7...
https://www.frontiersin.org/files/Articles/382815/fnins-12-0...
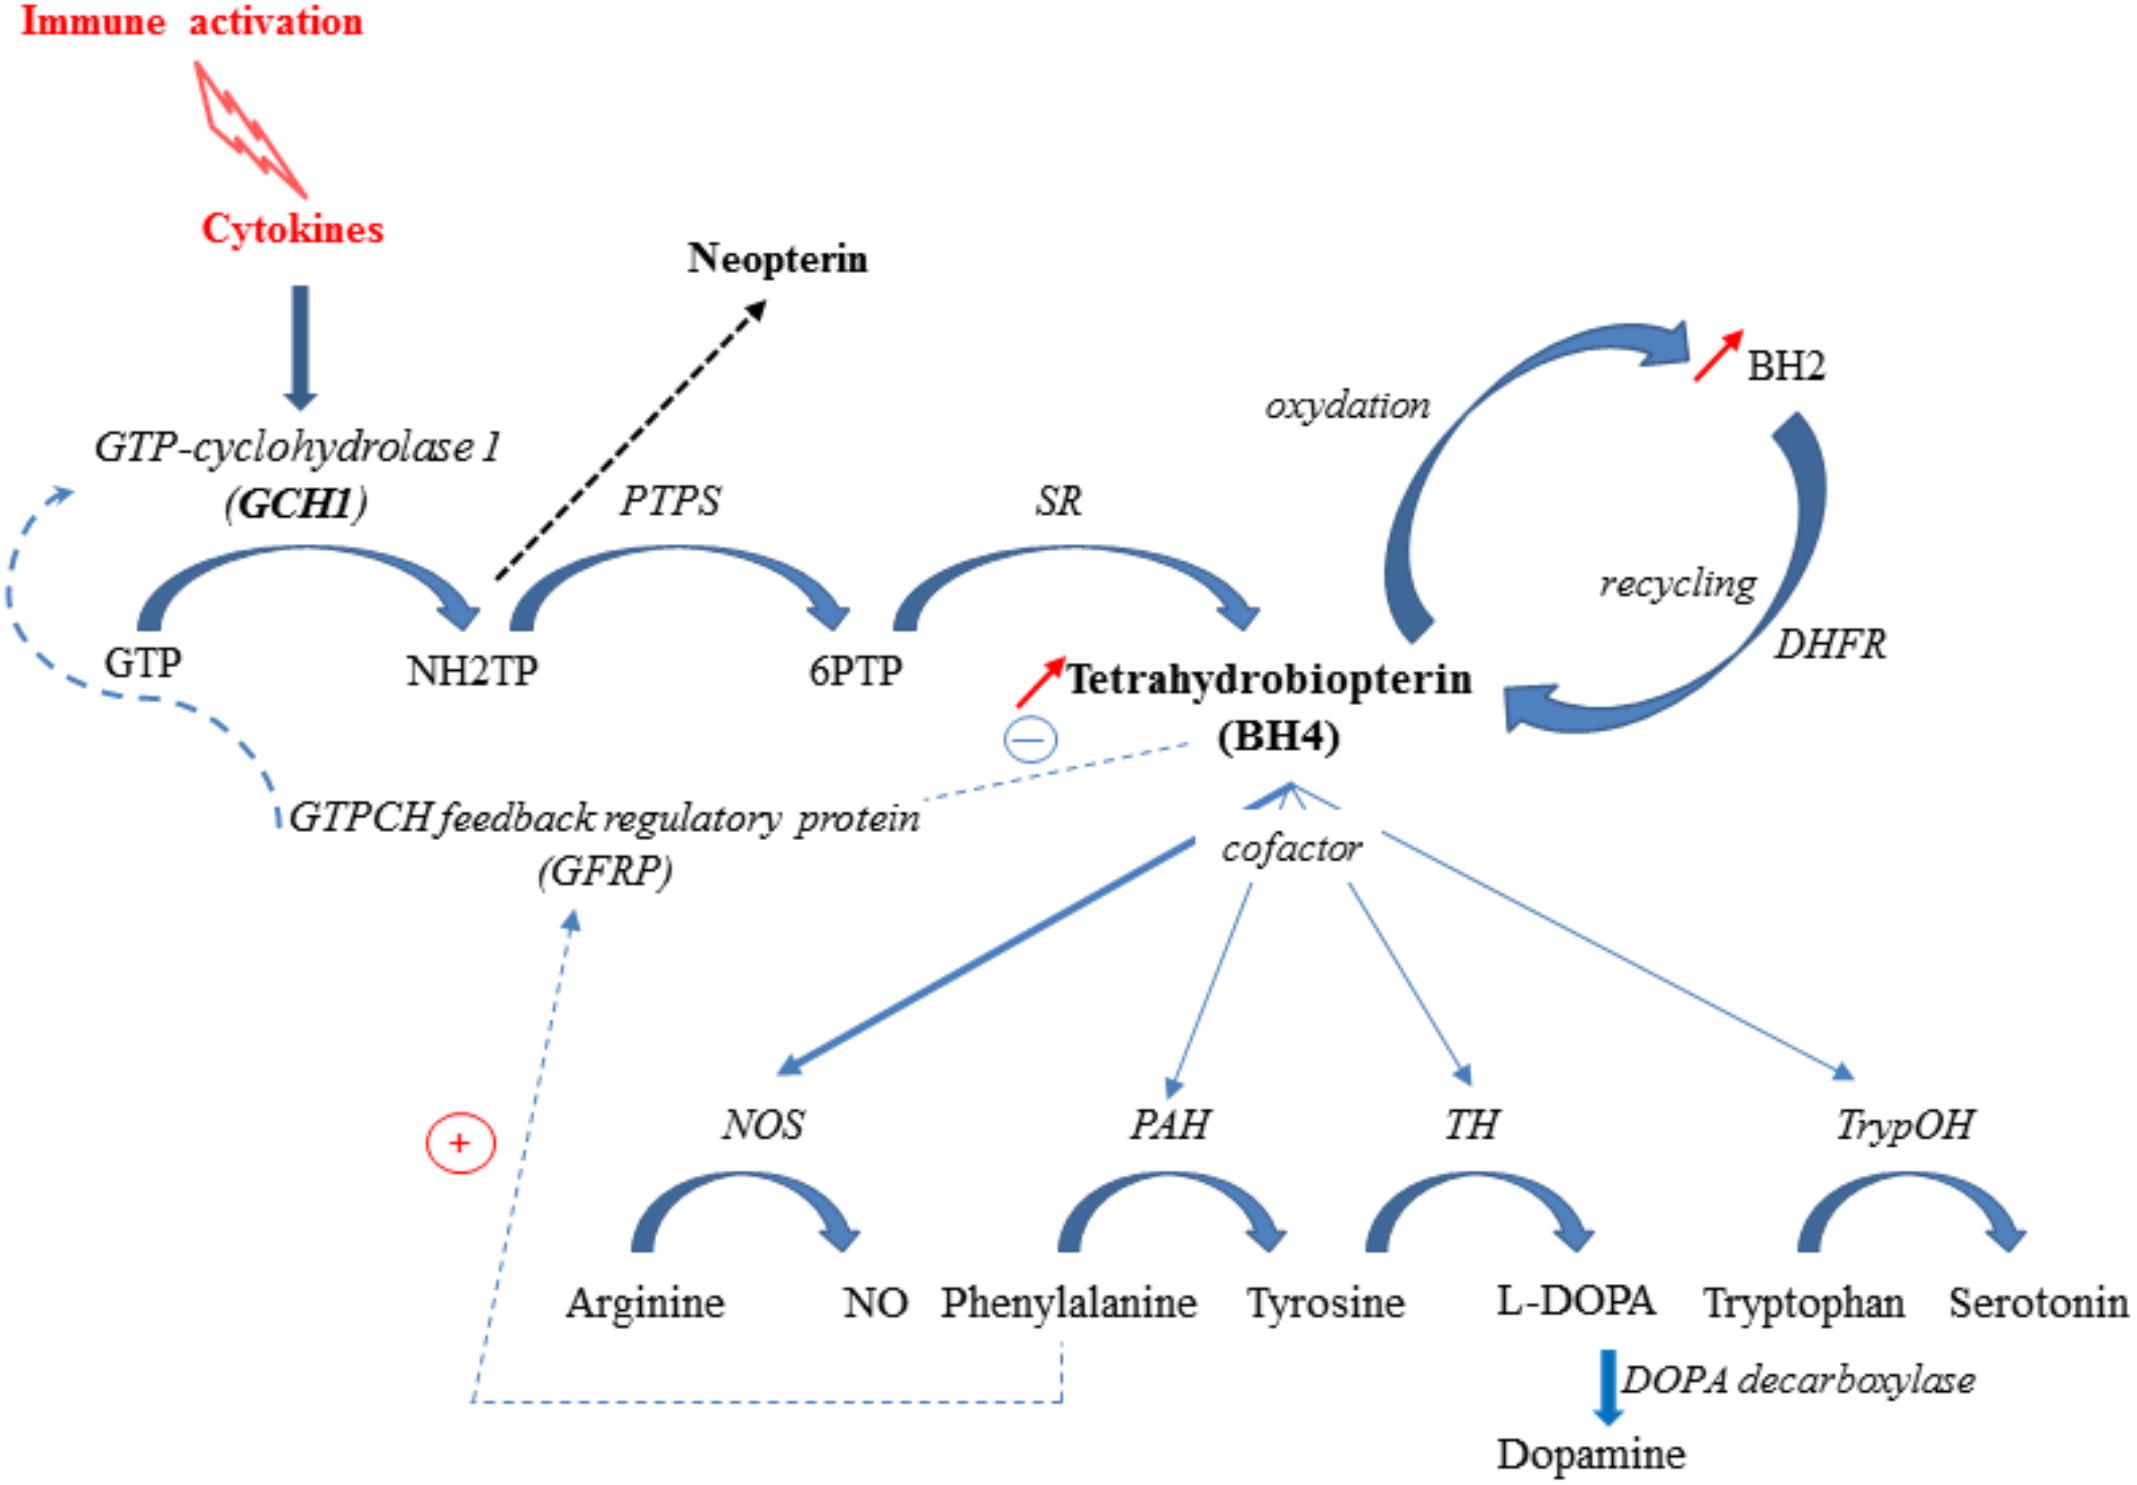
The deficiency causes problems with amino acid metabolism, which themselves mess up the brain.
The depression was a mere symptom of the underlying disease. When you read the DSM, you realize there are no mental illnesses, just syndromes: sets of signs and symptoms. Except in select few cases, the pathophysiology is unknown.
Protein is split into amino acids and then recombined into proteins inside body. The splitting process and recombination process need glucose in blood and, effectively, drain glucose from blood.
In my experience, some of the amino acid sport drinks can drain glucose from blood to the point where I had clear signs of very low glucose levels, including restlessness and shaking limbs.
The glucose level may affect mood and has other interesting effects.
If you look at what carbs, fats and proteins do with you mood, I think you will see that carbs make one relaxed (see relation between carbs and orexin), fats make one jolly (due to endocannabioids) and proteins make one awake (draining carbs from blood, mainly).
So what is this article saying? Me and my family just do not have perseverance? That we lack the "will" not to be depressed and anxious? That I just need to "Aspir[e] toward personal and career goals"? HA!
No, it's not true. You see, they found we all have a genetic disorder (GCH1 Deficiency). After I yelled at my doctors for years to look more deeply they finally found that it was not that I did not have goals, but that I needed a low protein diet and some medications that a psychiatrist could not give me, and now I am doing better. Now I can have goals.
So while this article might be true for some people with situational depression, I hate these studies because people always said crap like this to me. I was "lazy" and just needed a hobby, and on and on. They psychiatric association does not recognize, still, that mood disorders can be caused by metabolic issues. When they say I do not have enough serotonin and I ask them why they looked at me like they were in Psych 101. And these articles make psychiatrists lazy, putting all the effort on the patient while they sit back and collect check after check.