As others have mentioned, John Edwards had great success as a lawyer suing over cerebral palsy, claiming that it was caused by actions during delivery. While possible, most cases are caused by other factors such as infections, IVF, or low birthweight.
At trial, you have a sympathetic plaintiff with large needs vs a "rich" doctor and hospital. They might have caused this, they have insurance. So you systematically get very large verdicts against defendants who are unlikely to have done anything wrong. Edwards was very good at theatrics and not good on science.
Trials that rely on science and math are not great to take to a jury. Even discussions here get emotional when you deal with subjects like appropriate risk analysis and tradeoffs. Saying that you have a formula to only fix defects that kill more than x people or cost less than y per life saved is a great way of losing at trial and getting destroyed in a thread. It's also how every company and government makes decisions around safety - where stop signs go, guardrails, drug approval, armor in tanks...
Getting tort law right is hard - you want true injuries to be compensated but discourage people that are looking for lottery tickets.
We live in a country of 300 million people. Every permutation of things that can happen has happened. But that doesn't mean that large verdicts "where no or minimal injury was suffered" happen often enough to account for a significant share of medical malpractice payouts.
There was a Harvard study that looked at this issue pretty systematically, and concluded that the idea of "systematically" "large verdicts against defendants who are unlikely to have done anything wrong" does not fit the data: http://archive.sph.harvard.edu/press-releases/2006-releases/.... Most importantly, claims are about as likely to get denied despite the presence of error as they are to get paid despite the absence of error. (So improving the accuracy of the system would not necessarily decease payouts.)
The doctors/soon-to-be-doctors I've talked to/read aren't worried about the amount of money that leaves hospitals in malpractice payouts. They're worried that it's too easy to sue a doctor / hospital over arbitrary fabricated bullshit and win.
In states with a cap on the maximum medmal claim, the cap often "saves" the defendant money in situations where docs/hospitals really did screw up badly. But that cap has not effect on small, frivolous lawsuits where the doc/hospital weren't at fault.
$6 million verdict that was still being fought in the courts many years later rather than simply paid.
Oops, the reality: Trial #1: The woman was determined to be 90% at fault for her baby's problems, the law here doesn't let you collect if you're found more than 50% at fault. Trial #2, this time filed in the name of the baby. Still 90% to the woman. However, the jury assigned 5% to one doctor who examined her once several hours before the birth. He's the only one with anything, the whole $6 million verdict landed on him.
If that's what the lawyers consider a good case...
I think my takeaway from that analysis was that doctors are just as illogical as everyone else when it comes to things that aren't medicine. So you shouldn't really be surprised that they're unduly influenced by large, visible, and rare lawsuits, because that's how everyone works psychologically.
The correct place to look is not the perception of doctors, but the conclusions from actuarials in the setting if insurance rates.
If it was just a perception bias in the doctors, then it wouldn’t be reflected in the insurance premiums.
(1) Your insurer will usually prefer to settle rather than go to court, it's cheaper, so fuck your defense.
(2) You still take the reputational and emotional hit of being sued.
People discussing this rarely seem to get that docs are far more emotional about this than the money at risk merits. There are many things in play beyond "I don't want to lose a lawsuit." We really do get very upset about malpractice suits, for many reasons beyond our premiums going up.
There's also the risk of losing right to practice medicine - that is, being banned from providing the very service you spent the best part of your life specializing in.
Not a bad suggestion but resolving regulatory overhead by instituting regulation is a bit, suboptimal, IMHO.
The better solution is to reduce costs of the tests themselves:
https://news.ycombinator.com/item?id=17620197
In the software world, we have enjoyed significant productivity boost using Git/Hg/FOSSIL vs. CVS/SVN.
Branching in CVS/SVN was so expensive that people rarely do it. It takes me 2 seconds to branch in Git/Hg/FOSSIL
The Danish approach.
https://www.propublica.org/article/how-denmark-dumped-medica...
Could you read a little more about that case?
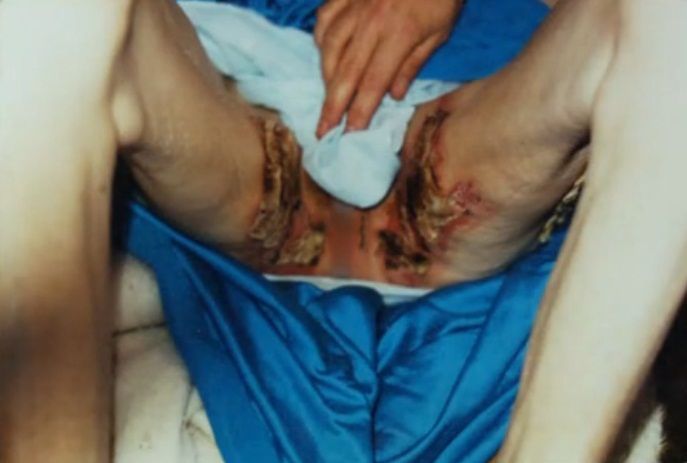
1) McDonald's had burned hundreds of people by that point, as the plaintiff's lawyer said in "Hot Coffee", "they were on notice." They served it that hot IIRC because it would stay hot slightly longer, even though lowering the serving temperature a tiny amount reduced burning disproportionately and would have prevented that and hundreds of other accidents.
2) The server didn't actually attach the lid to the cup.
3) She had horrible burns, 3rd degree.
4) McDonald's received an offer to pay for her ~$10,000 medical expenses, and counter-offered $600.
5) This was an old lady who had never sued anyone in her life.
6) She ultimately gave up on life in her old age because of the shaming.
"Hot Coffee" opened my eyes about the whole matter. I suggest you watch it.
They made it dangerously hot because it was marginally more profitable.
At trial they claimed they served it that hot because people wanted it to be hot when they arrived at their destination, but their own research showed that people consumed their food, including coffee, during their commute.
https://qph.fs.quoracdn.net/main-qimg-4820c7e31a90a1b89482c6...
and http://www.gruberlawgroup.com/wp-content/uploads/2016/04/ste...
The telling thing about laws to address malpractice liability is that they typically are focused on capping large verdicts. But such laws are illogical: generally, large verdicts will be awarded where a doctor screwed up and caused the most damage. Cases with large verdicts are the most meritorious ones, and the ones where limiting liability is least likely to eliminate over-testing that does not contribute to quality of care.
If states actually wanted to address the costs of defensive medicine, they would do something like create affirmative defenses for doctors who adhered to certain established testing protocols.